Every woman should receive respectful, understandable, culturally appropriate information about the indication, benefits, risks and alternatives to caesarean birth before the consent.
The operating team should be matched to surgical risk before transfer to theatre. Suspected PAS or complex repeat caesarean delivery requires senior multidisciplinary input.
Regional anaesthesia should be offered in preference to general anaesthesia.
Acidaspiration prophylaxis should follow the anaesthetic protocol.
Prophylactic antibiotics should be administered before skin incision using the locally approved regimen.
All women should undergo VTE risk assessment. Hydration, early mobilisation and mechanical and/or pharmacological prophylaxis should be used according to risk level and local policy (Please refer to Guideline on Prevention and Treatment of Venous-Thromboembolism in Obstetrics and Gynaecology in Sri Lanka, 2025 published by SLCOG).
Continuous one-to-one observation is required after neuraxial anaesthesia until haemodynamically stable; general anaesthesia requires observation until airway control and communication are restored.
Postoperative analgesia should be opioid-sparing where possible: regular paracetamol plus an NSAID unless contraindicated, with short-course rescue opioids only when needed.
The urinary catheter should be removed when the woman is mobile after regional anaesthesia, but not earlier than 6 hours.
4. Risk stratification and team allocation
Risk stratification must be completed before elective LSCS and as early as possible after the decision for emergency LSCS.
Use this guide during preoperative planning and at the time of decision for LSCS. Identify the level of surgical expertise accordingly. Move to a higher level when uncertainty exists or when clinical risk evolves.
Level I: Standard caesarean delivery
Table 4
Required team/resources
Clinical examples
Experienced postgraduate trainee, Medical Officer/ senior house officer under the supervision of a Consultant Obstetrician.
Breech, transverse lie or unstable lie; multiple pregnancy; posterior low-lying placenta; repeat caesarean delivery <=3 with no suspected placental abnormalities; maternal request; maternal infection such as primary genital herpes or HIV; diabetes with polyhydramnios or fetal macrosomia; fetal anomaly; previous major shoulder dystocia or previous third-/fourth-degree tear.
Level II: Specialist caesarean delivery
Table 5
Required team/resources
Clinical examples
Consultant obstetrician.
Blood products immediately available for anterior placenta praevia or high haemorrhage risk.
Urology/general surgery available as required.
Placenta praevia; lower-segment fibroid; very premature caesarean birth <28 weeks for severe FGR requiring possible classical incision; repeat caesarean delivery >=4; repeat caesarean delivery with ultrasound/MRI evidence of major lower-segment remodelling; prior major abdominal, bladder, bowel or uterine reconstruction surgery; patients with renal transplant or pelvic kidney.
Senior Obstetrician experienced in PAS surgery or Two Consultant Obstetricians.
Senior Anaesthetist; immediate blood products; neonatal team; HDU/ICU access.
Urology/general/vascular/interventional radiology support according to anticipated complications.
Placenta praevia covering the cervix in a woman with previous caesarean delivery; anterior low-lying placenta or placenta praevia with ultrasound/MRI evidence of major lower-segment remodelling; low-lying placenta or placenta praevia with imaging signs of PAS.
5. Preoperative assessment and preparation
5.1 Informed consent and shared decision-making
Confirm the clinical indication and urgency category for LSCS (Annexure 3).
Explain the procedure, anaesthetic options, expected recovery pathway and implications for the baby and future pregnancies.
Explain risks and benefits in language the woman can understand.
The language used in any information (written or oral) should be respectful and suitable for the woman, avoiding clinical jargon, taking into consideration of any personal, cultural or religious factors.
Encourage free discussions and support autonomous decision-making.
For maternal-request caesarean birth or severe anxiety/tocophobia, offer senior obstetric review and perinatal mental health support where time permits.
Use Annexure 1 as a structured counselling aid when discussing comparative risks of caesarean and vaginal birth.
5.2 Medical history and clinical examination
Table 7
Assessment domain
Minimum required content
Obstetric history
Parity, previous caesarean births, previous uterine surgery, previous PPH, placenta praevia/PAS risk, indication for current LSCS and urgency.
Medical history
Diabetes Mellitus, hypertension/pre-eclampsia, cardiac disease, asthma/respiratory disease, renal disease, bleeding or thrombotic disorders, sepsis, recent pyrexia and other relevant comorbidities.
Anaesthetic history
Previous spinal/epidural/general anaesthesia, difficult airway, aspiration risk, anaesthetic complications, neuraxial contraindications, anticoagulant timing and family history of anaesthetic complications.
Medication and allergy review
Current medicines, antiplatelets/anticoagulants, insulin or oral hypoglycaemics, antihypertensives, steroids and documented drug/latex/skin-prep allergies.
Temperature, pulse, blood pressure, respiratory rate, oxygen saturation and level of consciousness. Use MEOWS chart where available.
Abdominal/obstetric assessment
Fundal height, fetal lie/presentation, uterine tenderness, contractions, scar tenderness where relevant, fetal heart rate and antenatal records on placental location.
Cardiorespiratory assessment
Focused cardiovascular and respiratory examination for women with comorbidities, symptoms or abnormal vital signs.
5.3 Essential investigations
Table 8
Investigation
Indication
Full blood count
To identify any anaemia and thrombocytopaenia.
Assess haemoglobin and platelet count before surgery. Repeat if there is bleeding, pre-eclampsia, sepsis, anaemia or recent clinical deterioration.
Blood group and save and crossmatch whenever necessary
Prepare for potential transfusion needs required for LSCS.
Follow the local protocols for grouping and crossmatch according to haemorrhage risk, anaemia, placenta praevia/PAS risk, multiple previous caesareans or local transfusion policy.
Infection screening
Update HIV, syphilis and Hepatitis B nationally recommended antenatal infection screens if not previously completed or if results are unavailable.
Ultrasound information
Document fetal lie and presentation, placental site, estimated fetal weight where relevant and any suspicion of PAS or lower-segment complexity.
ECG
ECG if clinically indicated.
Additional tests
Individualise: renal/liver profile, coagulation, blood glucose/ketones, pre-eclampsia bloods, crossmatched blood products or imaging depending on clinical risk.
5.4 Family planning and contraception
Before planned LSCS and emergency LSCS where feasible, review postpartum contraception and family-planning preferences. Document counselling on birth spacing, future pregnancy risks after caesarean birth and any agreed method such as postpartum intrauterine contraception or sterilisation.
5.5 Anaesthetic consultation and planning
Refer high-risk women to the anaesthetic clinic or consultant anaesthetist well before the planned date of LSCS whenever possible.
For urgent/emergency LSCS, ensure early anaesthetic review once the decision for LSCS is made. Collaborate with anaesthetists to choose the safest and most appropriate mode of anaesthesia.
Patient Education: Inform about anaesthesia options.
Offer regional anaesthesia in preference to general anaesthesia. General anaesthesia should be reserved for maternal preference after counselling, contraindication or failure of regional anaesthesia, clinical urgeny or other clinical indications (E.g; Deformities of the vertebral column).
Discuss expected sensations (touch, pressure, pain) during regional anaesthesia.
Explain possibility of conversion to general anaesthesia, postoperative analgesia, post procedure shivering, vomiting and monitoring requirements.
Ensure a standard difficult airway management plan and availability of airway management equipment for all obstetrics patients recieveing general anaesthesia.
5.6 Preoperative preparation checklist
Table 9
Task
Standard action
Fasting
6 hours for solid food and 2 hours for clear fluids (excluding milk), unless urgency requires modified anaesthetic risk management.
Aspiration prophylaxis
Give histamine (H2) receptor antagonists or PPI and prokinetic agents.
For elective LCSC:
Ranitidine 150 mg oral or omeprazole 20 - 40 mg oral, minimum of 2 doses with an 8-10 hour gap in between doses, second dose 2 hours before the LSCS.
Add metoclopramide 10 mg oral with the second dose of the above.
For emergency LSCS :
Ranitidine 50 mg diluted in 10 ml distilled water slow IV or omeprazole 40 mg IV with metoclopramide 10 mg slow IV are to be given at the time of decision making.
0.3M Na citrate 15 ml orally should be given at theatre 30 mins prior to anesthesia.
(Medication and doses may change according to availability).
Medication management
Continue essential medicines unless contraindicated. Adjust insulin, oral hypoglycaemics, anticoagulants, antiplatelets and antihypertensives according to anaesthetic/obstetric and haematologist plan.
IV access
Placement of an intravenous (IV) cannula 16- 18 G for fluid administration is preferably done in OT for elective cases
Urinary catheter
Placement of a Foley catheter to drain the bladder in OT under anaesthesia and monitor urine output.
Skin preparation
Use 2% chlorhexidine skin preparation unless contraindicated. Use an approved alternative in case of an allergy.
In elective LSCS, it is a good practice to advice the patient to have a bath with soap and clean water prior to the commensement of surgical preparations.
Vaginal preparation
For ruptured membranes, consider aqueous povidone-iodine vaginal preparation to reduce endometritis risk; use aqueous chlorhexidine if povidone-iodine is unavailable or contraindicated.
Sedation and bowel preparation
Avoid routine maternal sedation and routine bowel preparation, according to ERAS. Use only for clear clinical indications.
Patient preferences
Where safe, accommodate a companion and patient preferences such as music,prayers or immediate bonding practices.
5.7 Prophylactic measures
Table 10
Risk area
Required action
Antibiotic prophylaxis
Administer prophylactic antibiotics before skin incision. Preferably IV cefuroxime 1.5g or IV co-amoxiclav 1.2g. In case of a penicillin allergy, use IV clindamycin 600 mg single dose.
Use the hospital-approved regimen active against endometritis, urinary-tract infection and wound infection. Record drug, dose and time.
Repeat the antibiotics if operative duration exceeds 4 hours or estimated blood loss >1500 mL.
(Please refer to Empirical and Prophylactic use of Antimicrobials, National Guidelines, Sri Lanka, 2024)
Thromboprophylaxis
Complete VTE risk assessment for every woman. Use hydration, early mobilisation, mechanical prophylaxis and LMWH according to risk and local policy.
Use pharmacological prophylaxis after bleeding-risk review and consultation of the obstetrician.
(Please refer to Guideline on Prevention and Treatment of Venous-Thromboembolism in Obstetrics and Gynaecology in Sri Lanka, 2025 published by SLCOG).
Hypothermia prevention
Maintain normothermia. Warm IV fluids and blood and blood products when volumes are significant and use warming measures when massive transfusion is indicated.
Haemorrhage readiness
For high-risk cases, ensure cross-matched blood, uterotonics, tranexamic acid access, cell salvage where available, senior help and massive transfusion activation pathway.
Prevention of neonatal anemia
Delayed cord clamping unless contraindicated and if time permits in prematurity.
5.8 Psychological and social support
Provide calm, consistent information and reassurance, especially for emergency LSCS.
Screen for severe anxiety, previous traumatic birth, perinatal mental health concerns, safeguarding issues and domestic violence risk when clinically appropriate.
Support Person: Accommodate the presence of a birthing partner during preparation and, if possible, during the procedure.
Use interpreter support where language barriers exist.
5.9 WHO surgical safety checklist and theatre handover
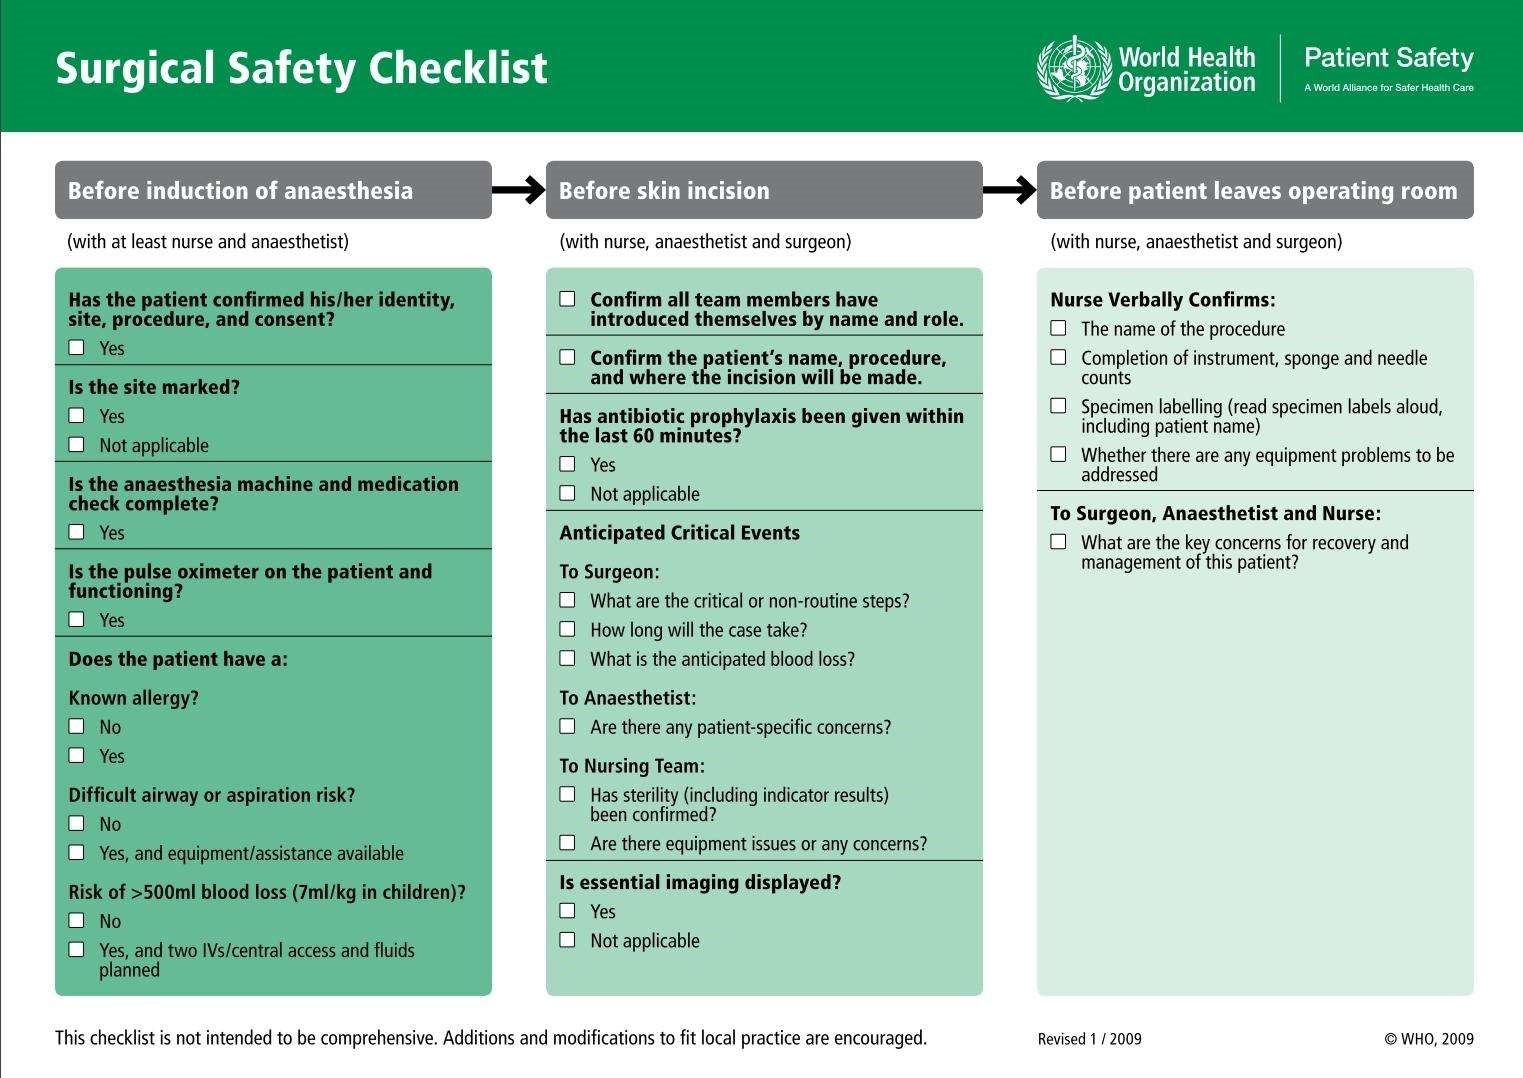
The WHO Surgical Safety Checklist, adapted for local caesarean practice, must be completed at three points: before induction of anaesthesia, before skin incision and before the woman leaves the operating room. Use Annexure 2 as the standard checklist framework.
6. Immediate postoperative care
6.1 Transfer from theatre and structured handover
Before transfer from theatre to recovery or ward, the operating, anaesthetic and nursing teams should complete a structured handover. Minimum handover content is shown below.
Table 11
Domain
Handover content
Procedure and indication
Type of LSCS, urgency category, intraoperative findings and any additional procedure performed.
Anaesthesia
Type of anaesthesia, neuraxial opioid used, airway concerns, conversion to general anaesthesia and plan for monitoring.
Haemorrhage and fluids
Estimated blood loss, uterotonics, tranexamic acid, IV fluids, transfusion, urine output and ongoing bleeding concerns.
Wound and drains
Skin closure method, dressing type, drains if any and wound-specific instructions.
Medications
Antibiotics given, analgesia plan, VTE prophylaxis plan, antiemetics, antihypertensives/ hypoglycemic agents and medications to withhold/ restart.
Baby and breastfeeding
Neonatal condition, skin-to-skin contact completed or deferred, breastfeeding initiation and neonatal review needs.
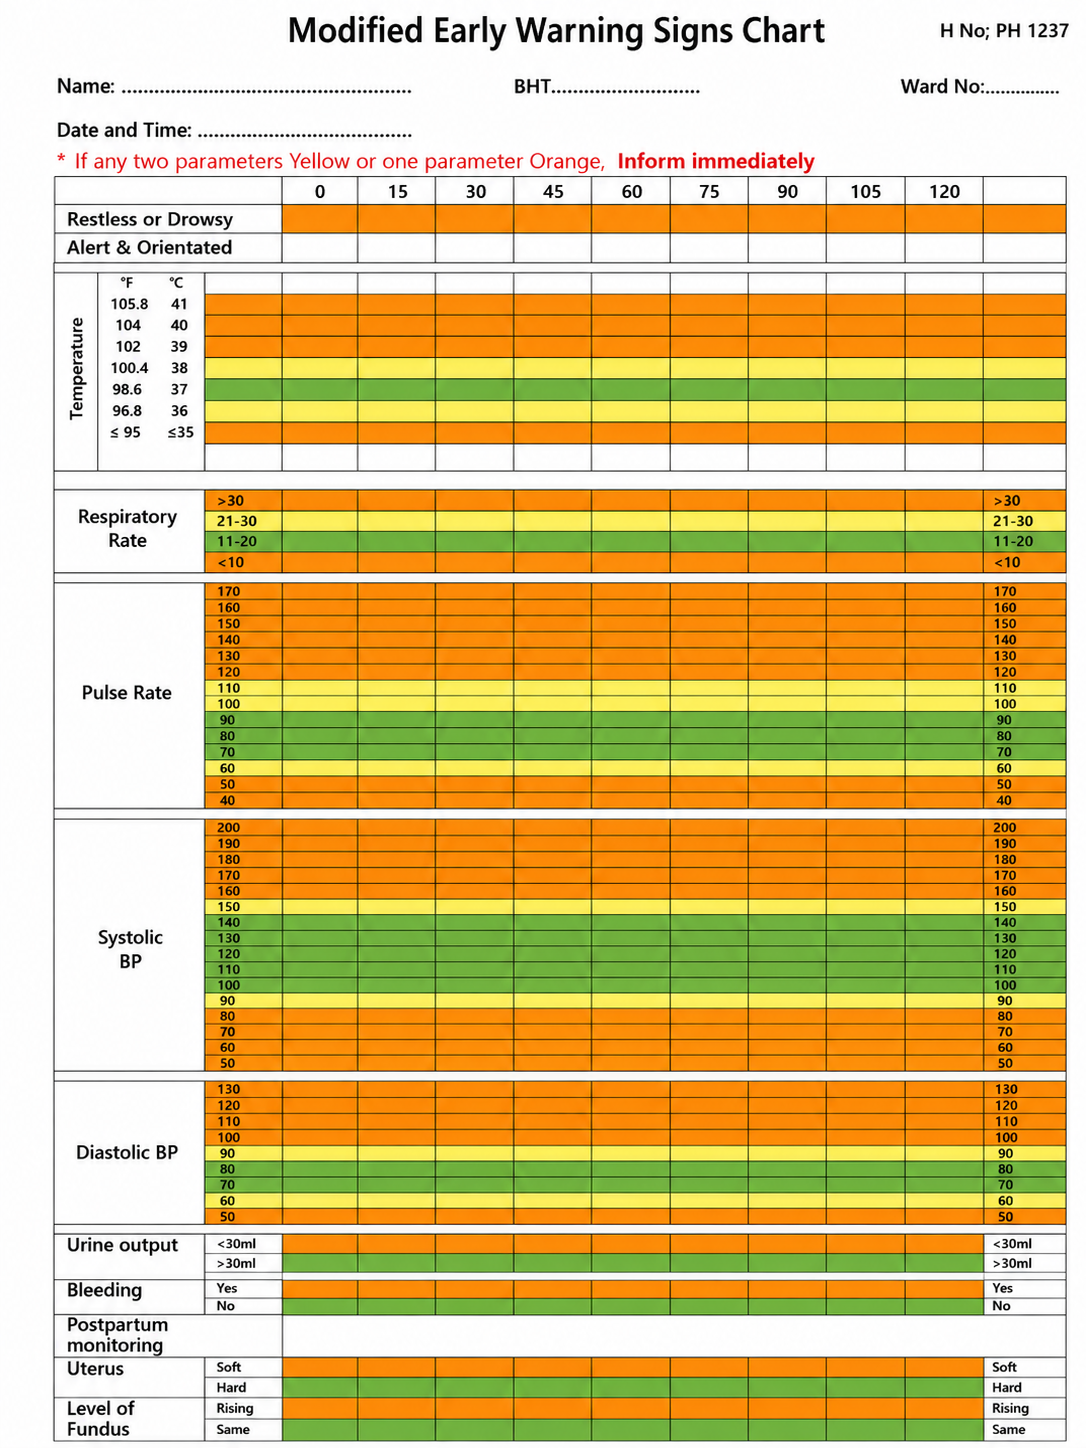
Continuous one-to-one observation until haemodynamically stable with regards to pulse, blood pressure and oxygen saturation. Then continue observations according to MEOWS chart (Annexure 4).
After general anaesthesia
Airway-skilled healthcare professional to provide continuous one-to-one observation until airway control is regained and the patient is able to communicate.
Monitor vitals (oxygen saturation, heart rate, blood pressure) frequently for 30 minutes , every 15 minutes for 2 hours every 30 minutes for 2 hours.
After intrathecal/epidural opioid with respiratory-depression risk factors
Hourly oxygen saturation, respiratory rate and sedation score for at least 12 hours, then routine postnatal observations unless clinical concerns persist.
Actively look for haemorrhage, uterine atony, sepsis, anaesthetic complications, urinary retention/injury, thromboembolism and severe pain requiring reassessment.
6.3 Pain management
Use Multimodal Analgesia. Prescribe baseline analgesics regularly rather than only as required.
Table 13
Step
Preferred approach
1. Baseline analgesia
Use a combination of analgesics according to the patient requirement to manage pain while minimizing side effects.
Subsequent analgesics can be added in the following order.
Paracetamol preparation 1g 6 hourly after oral intake initiated (Ibuprofen 400mg tds is an alternative).
Diclofenac Na 50 - 100 mg PR at theater if no contraindications or allergies. Subsequently 50mg up to 3 times a day.
NSAIDs should be avoided or used with caution in women with active bleeding or high haemorrhage risk, renal impairment, severe pre-eclampsia with renal involvement, thrombocytopaenia or platelet dysfunction, active peptic ulcer disease, NSAID allergy, asthma or other relevant contraindications. Consider gastric protection in women at increased gastrointestinal risk.
2. Rescue Analgesia
Oral Tramadol 50 mg up to 3 times a day.
S/C Morphine 0.1 mg/kg PRN (max 6 hourly). Add Ondansetron 4-8 mg 8 hourly.
For breakthrough pain, inability to tolerate oral medication or after general anaesthesia, consider IV/IM/SC morphine or IV PCA according to anaesthetic pain protocol. Monitor oxygen saturation, respiratory rate, sedation and pain score hourly while PCA is running and for at least 2 hours after stopping.
4. Side-effect prevention
Prescribe antiemetics when needed and laxatives for women receiving opioids.
Reassess pain score, sedation score, respiratory rate, oxygen saturation and urine output before escalation of analgesia.
Severe, worsening or atypical pain should prompt clinical reassessment to exclude haemorrhage, sepsis, urinary retention, urinary tract injury, bowel injury, wound haematoma or thromboembolism.
5. Dexamethasone
Unless contraindicated, give dexamethasone 8 mg IV after delivery as part of multimodal analgesia and postoperative nausea and vomiting reduction.
For women with diabetes or gestational diabetes, monitor capillary blood glucose postoperatively and manage according to the postpartum diabetes plan.
For LSCS under general anaesthesia
The transversus abdominis plane block (TAP block) represents a suitable regional analgesic modality following LSCS under general anaesthesia.
Local anaesthetic wound infiltration serves as a practical alternative.
6.4 Early mobilisation and VTE prevention
Encourage leg movements and sitting up as soon as safe after anaesthesia has resolved.
Support early ambulation once haemodynamically stable and motor block has resolved.
Use hydration, mobilisation and Thromboembolic deterrent stockings (TEDS) for women at increased risk. Use LMWH according to VTE risk assessment (Please refer to Guideline on Prevention and Treatment of Venous-Thromboembolism in Obstetrics and Gynaecology in Sri Lanka, 2025 published by SLCOG).
Pay particular attention to leg pain/swelling, chest pain, cough, shortness of breath, unexplained tachycardia or desaturation; escalate immediately if VTE is suspected.
6.5 Urinary catheter and bladder care
Maintain accurate urine-output monitoring during immediate recovery.
Remove the urinary catheter after 6 hours from the regional anaesthesia once the woman is mobile. Maintain UOP more than 0.1mg/kg/hr.
After catheter removal, document the first void and assess for urinary retention, dysuria, haematuria or symptoms suggesting urinary tract injury or infection.
6.6 Wound care and hygiene
Table 14
Area
Standard
Dressing
Keep the wound clean and dry. For standard dressings, remove between 18 - 24 hours after caesarean birth according to wound condition and local policy.
High BMI / high wound-risk
Consider negative-pressure wound therapy after caesarean birth for women with BMI ≥ 35 kg/m² to reduce wound infection risk
Daily review
Monitor for fever, increasing pain, redness, swelling, discharge, separation or dehiscence.
Patient advice
Wear loose clothing and cotton underwear. Clean with water and soap and dry the wound daily after dressing removal.
Suture/clip removal
Plan removal if non-absorbable sutures or clips are used.
6.7 Fluid, nutrition and glycaemic care
Maintain appropriate fluid balance; avoid unnecessary prolonged IV fluids once oral intake is adequate.
Monitor for signs of fluid overload or deficit
If recovery is uncomplicated, allow normal eating and drinking as tolerated. Early oral intake may be offered within 2 hours when nausea, vomiting, haemorrhage, bowel injury or other contraindications are absent.
For women with diabetes or gestational diabetes, restart or adjust glucose monitoring and treatment according to the postpartum diabetes plan. Avoid both hyperglycaemia and hypoglycaemia.
Treat postoperative nausea and vomiting promptly to facilitate hydration, feeding and mobilisation.
6.8 Breastfeeding, bonding and neonatal care
Prior to LSCS neonatal preparedness must include:
Indication for paediatric attendance (preterm <37 weeks, suspected fetal compromise, meconium, multiple pregnancy, congenital anomaly, Category 1 or 2 urgency).
Resuscitation equipment checks and warm cot availability.
Communication with neonatal team for high-risk cases.
Post LSCS neonatal care includes:
Offer and facilitate early skin-to-skin contact whenever maternal and neonatal condition permits.
Support the first breastfeed as soon as possible.
Provide assistance with breastfeeding positions and address any lactation difficulties.
6.9 Education and discharge planning
Discharge readiness requires both clinical stability and clear safety-netting. Women recovering well, apyrexial and without complications may be suitable for discharge after 24 hours where;
Home follow-up and local postnatal pathways are reliable
The woman has phone access and transport to hospital if needed
Table 15
Discharge domain
Minimum discharge content
Clinical stability
Stable vital signs, controlled pain on oral medication, no excessive bleeding, uterus well contracted, mobilising safely, tolerating oral intake and no unresolved anaesthetic/surgical concern.
Wound and hygiene
Written and verbal wound-care instructions, red-flag symptoms and plan for suture/clip removal if needed.
Medicines
Analgesics with breastfeeding advice, VTE prophylaxis if prescribed, antihypertensives/diabetes medication changes and constipation/antiemetic plan if needed.
Warning symptoms
Return urgently for heavy bleeding, fever, worsening abdominal/wound pain, offensive lochia, wound discharge/separation, chest pain, breathlessness, calf swelling/pain, severe headache, visual symptoms, seizures, collapse, difficulty passing urine or concern about the baby.
Follow-up
Postnatal follow-up plan, blood-test follow-up when required, infant follow-up, contraception plan and future-birth counselling after emergency/unplanned LSCS.
6.10 Mental health considerations
Be alert for postpartum depression, anxiety, traumatic birth response and fear related to emergency LSCS.
Offer debriefing after emergency or unplanned caesarean birth, including explanation of why LSCS was performed.
Escalate immediately for suicidal ideation, psychosis, severe agitation, safeguarding concerns or inability to care for self/baby.
Connect women to perinatal mental health services, counselling or social support pathways where needed.
7. Escalation criteria
Table 16
Escalate urgently if any of the following are present
Suggested immediate action
MEOWS red trigger or persistent yellow triggers (Annexure 4).
Call senior obstetrician, anaesthetist, senior obstetrics trainee or senior house officer and recovery/ward senior nurse; initiate ABCDE assessment; consider HDU/ICU.
Discharge counselling, warning symptoms, medications, contraception plan and follow-up arrangements.
8.2 Practical audit indicators
Table 17
Indicator
Numerator / denominator
Suggested target
Documented indication and urgency category
Number with documented indication and urgency / all LSCS
>=95%
Risk stratification completed
Number with documented surgical risk level / all elective and non-crash LSCS
>=90%
Consent documented
Number with documented consent discussion / all non-crash LSCS
>=95%
Antibiotics before skin incision
Number receiving prophylaxis before incision / all LSCS
>=100%
WHO checklist completed
Number with completed sign-in, time-out and sign-out
>=95%
VTE assessment documented
Number with VTE risk assessment / all LSCS
>=95%
Postoperative observations completed
Number with MEOWS/local recovery observations completed / all LSCS
>=95%
Wound-care and discharge advice documented
Number with documented advice / women discharged after LSCS
>=90%
9. Annexures
Annexure 1. Comparative risks to support informed consent
This table should be used as a counselling aid, not as a substitute for individualised risk assessment. Individual risks vary according to clinical indication, urgency, previous surgery, placental site, comorbidities, anaesthetic risk and neonatal factors.
Table 18
Comparative category
Examples
Risk associated with caesarean birth.
Maternal:
Major abdominal surgery - risks include bleeding, infection, blood clots (DVT).
Injury to bladder, ureter, or bowel (rare but possible).
Longer home recovery - 6–8 weeks before return to full activity.
Uterine scar affects all future pregnancies (placenta praevia, uterine rupture risk).
Each subsequent caesarean becomes technically more difficult.
Adhesions (internal scarring) - may cause future pain or surgical difficulty.
Increased risk of DVT / pulmonary embolism.
Neonatal:
Transient tachypnoea of the newborn (TTN / “wet lung”); if LSCS performed at 39 weeks, this risk is reduced but not eliminated.
Slightly higher chance of admission to Paediatric Baby Unit (PBU / SCBU).
Small risk of accidental surgical nick to baby’s skin during uterine incision (rare).
Benefits of caesarean birth
Maternal:
Planned, predictable timing, reduces anxiety about labour
Avoids risk of labour-related perineal injury.
Lower risk of urinary incontinence immediately after birth.
Avoids risk of emergency caesarean
May be the preferred option for certain medical conditions.
Neonatal:
Avoid neaonatal trauma from instrumental deliveries.
Low risk of meconium aspiration syndrome.
Risk associated with vaginal birth
Maternal:
Perineal tears (1st–4th degree) or episiotomy.
Pelvic floor damage - may contribute to later urinary or bowel leakage.
Prolonged or obstructed labour may require an emergency caesarean.
Instrumental delivery (forceps or ventouse) if progress is slow.
Shoulder dystocia
Perineal pain in the weeks after birth.
If labour does not begin naturally, induction of labour may be needed.
Risk of stillbirth (FDIU) increases gradually beyond 40–42 weeks while awaiting spontaneous labour.
Neonatal:
Meconium Aspiration Syndrome
Rare risk of skull fracture or nerve injury with instrumental delivery.
Shoulder dystocia can cause arm nerve injury (brachial plexus).
Cord prolapse (rare but serious).
Benefits of vaginal birth
Maternal:
Hospital stay is usually shorter; home recovery is much quicker - most women return to normal activity within 1–2 weeks.
No abdominal surgical scar or future scar-related complications.
Lower risk of injury to bladder, bowel, or major blood vessels.
Breastfeeding often easier to establish.
No uterine scar - better for future pregnancies.
Neonatal:
Passage through birth canal helps clear fluid from baby’s lungs.
Hormonal surges during labour help prepare baby’s lungs and stress response - reduced respiratory morbidity for the baby.
Exposure to vaginal bacteria - may support baby’s gut microbiome and immunity.
Immediate LSCS; aim for birth as soon as possible, usually within 30 minutes
Category 2
Maternal or fetal compromise, but not immediately life-threatening
Pathological CTG without persistent bradycardia, failed instrumental delivery, slow progress with fetal/maternal concern, worsening pre-eclampsia requiring urgent birth
Urgent LSCS; aim for birth as soon as possible, usually within 75 minutes
Category 3
No maternal or fetal compromise, but early birth is needed
Failed induction without distress, previous LSCS in early labour, malpresentation in labour without compromise
Early LSCS; but not emergency; timing based on theatre and clinical priorities
Category 4
Birth timed to suit woman or healthcare provider
Elective repeat LSCS, planned LSCS for placenta praevia/accreta spectrum when stable, breech planned LSCS
Elective LSCS; at scheduled time
Annexure 4. Modified Early Obstetric Warning Signs Chart
Figure from the source guideline
10. References
National Institute for Health and Care Excellence. Caesarean birth. NICE guideline NG192. Published 31 March 2021; last updated 10 June 2025. Available from: https://www.nice.org.uk/guidance/ng192.
Wilson RD, Caughey AB, Wood SL, Macones GA, Wrench IJ, Huang J, et al. Guidelines for antenatal and preoperative care in cesarean delivery: Enhanced Recovery After Surgery Society recommendations (Part 1). Am J Obstet Gynecol. 2018;219(6):523.e1-523.e15. doi:10.1016/j.ajog.2018.09.015.
Caughey AB, Wood SL, Macones GA, Wrench IJ, Huang J, Norman M, et al. Guidelines for intraoperative care in cesarean delivery: Enhanced Recovery After Surgery Society recommendations (Part 2). Am J Obstet Gynecol. 2018;219(6):533-544. doi:10.1016/j.ajog.2018.08.006.
Sultan P, Monks DT, Sharawi N, Bamber J, Panelli DM, Sauro KM, et al. Guidelines for postoperative care in cesarean delivery: Enhanced Recovery After Surgery Society recommendations (Part 3)-2025 update. Am J Obstet Gynecol. 2026;233(6S):S184-S198. doi:10.1016/j.ajog.2025.01.038.
World Health Organization. WHO Surgical Safety Checklist. Revised 1/2009. Geneva: WHO; 2009. Available from: https://www.who.int/teams/integrated-health-services/patient-safety/research/safe-surgery/tool-and-resources.
American College of Obstetricians and Gynecologists; Society for Maternal-Fetal Medicine. Placenta accreta spectrum. Obstetric Care Consensus No. 7. Obstet Gynecol. 2018;132(6):e259-e275. doi:10.1097/AOG.0000000000002983.
Royal College of Obstetricians and Gynaecologists. Placenta praevia and placenta accreta: diagnosis and management. Green-top Guideline No. 27a. BJOG. 2019;126:e1-e48. doi:10.1111/1471-0528.15306.
Sri Lanka College of Obstetricians and Gynaecologists; Sri Lanka College of Haematologists. Guideline on Prevention and Treatment of Venous-Thromboembolism in Obstetrics and Gynaecology in Sri Lanka. Guideline No. 1.0: ISBN: 978-955-9179-04-7. Available from: https://slcog.lk/guideline-on-prevention-and-treatment-of-venous-thromboembolism-in-obstetrics-and-gynaecology-in-sri-lanka/
Empirical and Prophylactic use of Antimicrobials, National Guidelines, Sri Lanka, 2024. Available from: https://slmicrobiology.lk/empirical-and-prophylactic-use-of-antimicrobials-national-guidelines-sri-lanka-2024/
Adshead D, Wrench I, Woolnough M. Enhanced recovery for elective Caesarean section. BJA Educ. 2020;20(10):354-357. doi:10.1016/j.bjae.2020.05.003.
Crowe G, Atterton B, Roofthooft E, Joshi GP, Rawal N, Wu C, et al. Pain management after elective caesarean section under neuraxial anaesthesia: an updated systematic review and procedure-specific postoperative pain management (PROSPECT) recommendations. Anaesthesia. 2026;81:819-839. doi:10.1111/anae.70141.