
1. Introduction
The aim of this guideline is to provide recommendations to healthcare providers in the management of a healthy woman with a single foetus in labour at term (37 weeks onwards). It does not cover the care of women with complicated pregnancies.
The objective of this guideline is to ensure optimal management of women in labour, detect any abnormality, take appropriate action, prevent complications and consequently make childbirth safer; and also to make sure that these women are treated with respect and compassion, kept well informed and well supported throughout the process of labour.
2. Diagnosis of labour
Labour is diagnosed by the presence of regular, painful, intermittent contractions, which are of increasing frequency, duration and intensity, leading to progressive cervical effacement, dilatation and expulsion of the conceptus.
Note: For the purpose of this guideline, labour is also diagnosed in the presence of painful contractions occurring at a frequency of 2 or more in 10 minutes.
Labour has four stages;
- First Stage
- Second Stage
- Third Stage
- Fourth Stage
Definitions
The first stage of labour subdivided to two stages;
i. Latent phase of the first stage of labour – From the commencement of labour to a cervical dilatation of 6 cm. (This is a period of time, not necessarily continuous, where there are painful contractions and some cervical changes including cervical effacement and dilatation up to 6cm takes place).
ii. Active phase of the first stage of labour – Commences at a cervical dilatation of 6 cm and ends with full dilatation (There are regular painful contractions and progressive cervical dilatation from 6cm up to full dilatation)1.
If the diagnosis of labour is uncertain, observation should continue and reassessment should be done four hours apart.
Any woman who is diagnosed as not being in labour, but continues to complain of pain, would require careful assessment by an experienced medical professional. Possible diagnoses of placental abruption and nonobstetriccauses should be considered.
In all cases of suspected labour, foetal condition should be assessed.
Second stage of labour is from the full dilatation of the cervix till complete delivery of the foetus.
Third stage of labour is from the delivery of the foetus till the end of complete expulsion of placenta.
Fourth stage of labour is the immediate 2 hours following the delivery of the placenta.
3. Management of labour
3.1. General considerations
3.1.1. Communication between woman and healthcare professionals/workers
- Greet the mother with a smile and a personalwelcome
- Treat her with respect and dignity
- Assure privacy
- Establish good rapport with the labouring womanasking her about her wishes and concerns. Address them meaningfully
- Maintain a calm and confident approach which willreassure women that the situation is under control
- Assess the woman’s knowledge of strategies forcoping with pain and provide balanced information to find out which available approaches are acceptable to her.
- Ask her permission before all procedures andobservations, focusing on the woman rather than technology or the documentation.
3.2. Cervical dilatation
Historical labour curve published in the 1950s by Friedman which divided latent and active phase of first stage at 4cm dilatation was replaced in 2010 by the publication of The Modern Labour Curve from the study of Zhang and colleagues1 which included 60000 patients from 19 hospitals in the United States with pregnancies at term who went on to have vaginal deliveries and normal perinatal outcomes. In that study both nulliparous and multiparous women progressed in a similar fashion up to 6cm of cervical dilatation.
After 6cm, the progress was more rapid (especially in multiparous women) hence indicating active phase of labour. They found that the active phase in nulliparous women took 1.4 to 2.2 hours for each centimeter and 0.8 to 1.8 hours in multiparous women.
In another study Wood and colleagues2 assessed 2000 patients regarding the risk of caesarean delivery in relation to cervical dilation on admission to labour ward when in spontaneous labour. Admission in the latent phase of labour of less than 6 cm was associated with increased risk of caesarean delivery, in comparison to women admitted with more than 6 cm of dilatation.
As stated in this study it is good to consider delaying admission to the labour ward of patients with intact membranes to reduce the risk of caesarean delivery especially when the dilatation is less than 6 cm.
3.2.1. Comparison of induced with spontaneous labour
| 4 cm → 10 cm | Median | Rate: 95th percentile | |
|---|---|---|---|
| Nulliparous | Spontaneous | 3.8 | 11.8 hr |
| Induced | 5.5 | 17 hr | |
| Multiparous | Spontaneous | 2.4 | 8.8 hr |
| Induced | 4.4 | 16.2 hr |
3.3. Descent of the presenting part Concomitant descent of the presenting part needs to happen during labour7
In general, multipara had higher positioning of the presenting part than nullipara at the first stage. However, findings of the study showed that 95% of all patients were either at zero or + at cervical dilation of 10 cm. Though slow descent is not completely abnormal at 10 cm of dilatation, foetal presenting part at stations higher than zero should arouse caution in management.
3.4. Special populations to consider regarding labour
1. Obesity
Obesity is an independent risk factor for caesarean delivery and complications of caesarean delivery as shown in a study by Norman and colleagues4 which subjected more than 5000 women at term who reached full cervical dilatation. The study considered 4 cm as the transition dilatation from the latent to active. However, the graphs given in the study showed this transition took place at 6 cm dilatation. The latent phase for obese women with a BMI greater than 30 was significantly longer. The higher the BMI, the more evident was the lag in latent phase. However, the active phase showed no difference.
2. Preterm labour
Preterm labour is a common condition (<37 weeks). Spain and colleagues5 studied a sample of 5000 women in preterm and term labour. The active phase of labour was observed to be faster in preterm labour and the transition still took place at 6 cm of dilatation.
3. VBACs (Vaginal birth after caesarean delivery)
Graseck and collegues10 compared term spontaneous labour without scar with VBACS. This study included 2000 patients. They found that the labour curves were no different in two groups.
3.5. General preparation for labour
- Shaving or trimming of perineal hair may be neces-sary to facilitate unhindered surgical performance and repair of the episiotomy.
- Efforts must be made to minimise faecal soiling.Where an enema is deemed necessary, a medicated enema is recommended.
(These two steps should not be considered mandatory)
- Women are encouraged whenever possible to havea companion of her choice during labour, depending on the facilities and clinical situation.
3.5.1. Documentation
- Admit the mother to the labour room and completethe ‘handing / taking over’ form.
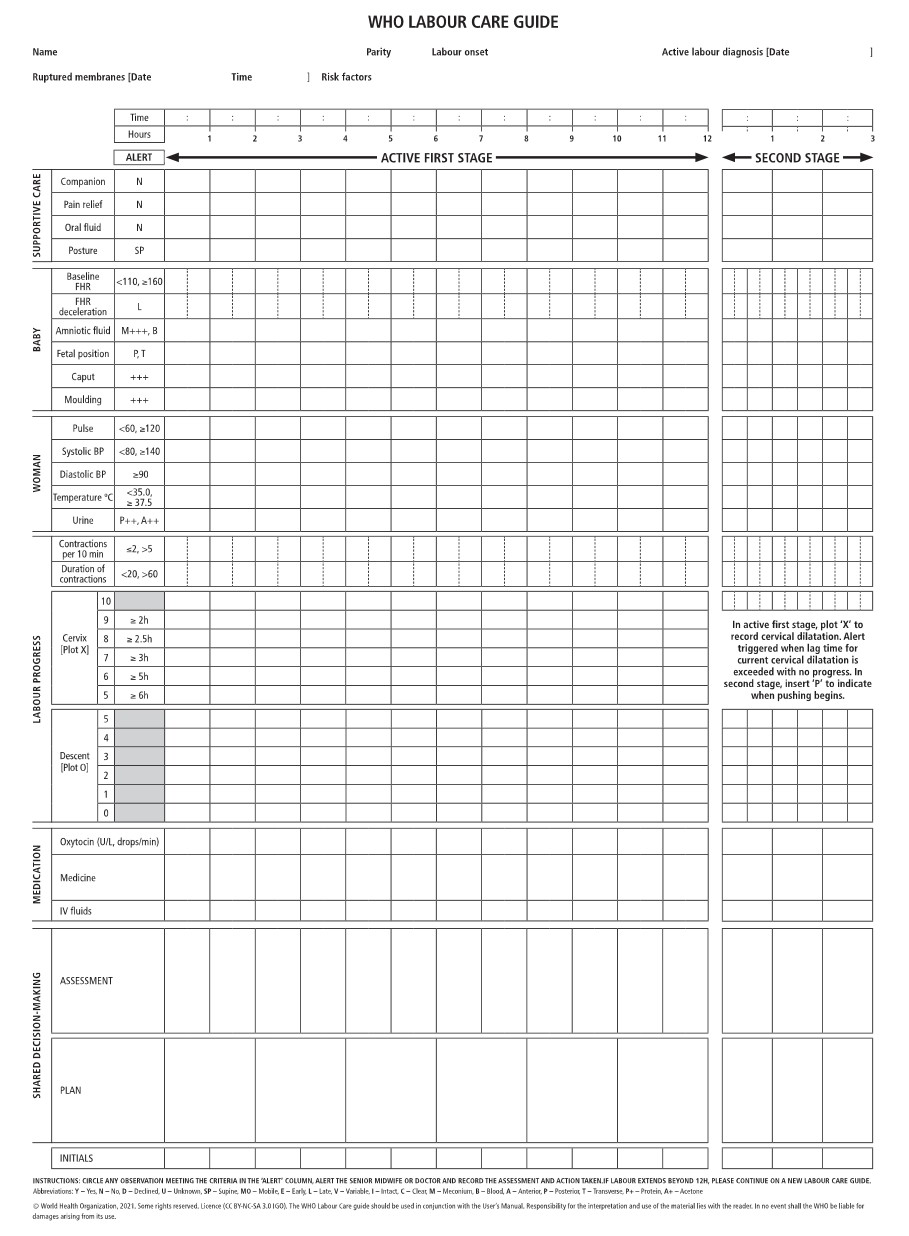
- Keep relevant notes on the BHT (Bed Head Ticket)and start a Labour Care Guide (Annexure 2).
- Review clinical notes and reassess risk factors.
- Accurate documentation of all observations andinterventions must be made with timing.
- All obstetric examinations and procedures carriedout must be documented in the clinical notes. Each entry must be accompanied by a plan for management and be signed by the responsible person.
3.5.2. Mobilisation and positioning
- Women should be encouraged and helped to moveabout and adopt whatever positions they find most comfortable throughout labour. (Supine position is considered less favourable due to effects on the venous return).
- They need to be encouraged to void urine regularly.
3.5.3. Eating and drinking during labour
- Mothers must be encouraged to consume clear,non-fizzy liquids during labour. Isotonic solutions such as oral rehydration fluid and coconut water are more beneficial than water.
- In addition to clear fluids, women in the latent phasemay consume light solids e.g. biscuits and fruits.
3.5.4. Hygiene during labour
- Mothers could be encouraged to have a shower inpreparation.
- Strict asepsis must be maintained during labour.
- Instruments should be available in sterile packets.
- Use proper hand washing technique.
- Use of double gloves and disposable gloves areencouraged when instrumental procedures are involved.
3.6. Management of the first stage of labour
3.6.1. Management of latent phase
It is important to recognize the duration of the latent phase of labour, since its prolongation could lead to maternal exhaustion, dehydration and acidosis, leading to eventual foetal compromise and dysfunctional labour.
Women in the latent phase of labour would be best managed in the antenatal ward.
Women in the latent phase of labour must be assessed on a regular basis, as follows:
- Check the foetal heart (Doppler instrument for thistask is ideal) and maternal pulse every half hour;
- Check temperature ever four hours;
- Consider vaginal examination depending on thecontraction pattern and initial cervical dilatation; (Keep in mind about the risk of introducing sepsis).
- Document the colour of amniotic fluid if themembranes rupture;
- Use of a sanitary pad may help with the detectionof early presence of meconium.
- Consider the optimal requirement for analgesia.
It is important to inform the mother that it is common to have slow progress in the latent phase and reassure her.
The latent phase is considered prolonged when it lasts more than 12 hours in a primigravida and 8 hours in a multigravida. In these situations, an experienced medical officer must reassess the mother with a view of possible augmentation of labour.
3.6.2. Management of active phase
3.6.2.1. General management
All pregnant women diagnosed as being in the active phase of the first stage of labour need to be admitted to the labour ward.
The initial assessment of a woman at the labour room should include:
- Listening to her story, considering her emotionaland psychological needs and reviewing her clinical records
- Physical observation: temperature, pulse, bloodpressure
- Length, strength and frequency of contractions
- Abdominal palpation: fundal height, lie, presentation,position and station
- Vaginal loss: show, liquor, blood
- Assessment of woman's pain including her wishesfor coping with labour along with the range of options for pain relief
- The foetal heart rate (FHR) should be auscultatedpreferably with a hand-held Doppler for a minimum of 1 minute immediately after a contraction every 15 minutes
- The maternal pulse should be recorded todifferentiate between maternal pulse and FHR
A vaginal examination should be offered whennecessary.
Health care professionals who conduct vaginal examination should:
- Be sure that there is a valid indication for vaginal examination and that it will add important information to the decision-making process
- Be aware that for many women who are likelyalready in pain, highly anxious state of mind and in an unfamiliar environment, vaginal examinations can be very distressing
- Ensure the receipt of woman’s consent as well asher privacy, dignity and comfort
- Explain the reason for examination and what will beinvolved
- Explain the findings and their impact sensitively tothe woman.
It is extremely important that delay in progress is assessed by an experienced medical officer. This assessment must consider:
- the uterine contractions
- descent and position of the foetal head
- features of early obstruction of labour (caput andmoulding), and
- the foetal condition.
In women with delay in the active phase of the first stage, every effort must be made to find a cause for the delay. This may either be due to inadequate contractions or obstruction due to CPD (Cephalopelvic Disproportion), malpresentation or malposition (such as occipito-posterior position), or a combination of these.
3.6.2.2. In cases of inadequate contractions;
This should have been identified and corrected before the diagnosis of arrest is made
- Amniotomy must be performed if membranes arestill intact.
- Following that, the woman must be reassessed intwo hours.
- In case there is inadequate progress, augmentationwith oxytocin should be considered.
- The situation must be reassessed after four hoursof active management or earlier if required.
3.6.2.3. Multiparous women with delayed progress:
- Must be viewed with extreme caution by anexperienced healthcare personnel.
- It is very important to exclude mechanical causesof delay before considering oxytocin.
- Use of oxytocin is contraindicated in multipara withany evidence of obstructed labour.
Attention must be paid to providing effective pain relief and correcting dehydration in these situations.
After paying attention to the above, caesarean delivery must be considered when the progress is diagnosed as arrested.
3.6.3. Diagnosis of arrest of active part of first stage of labour
Historical Friedman curve-based diagnosis of first stage arrest is done when there is no cervical change for more than 2 hours with adequate contractions and at least 4 cm of dilatation.
With the acknowledgement of current understanding of labour curve, the patient needs to be at least
6 cm dilated
- Have membranes ruptured
- With no cervical change for at least 4 hours of adequate natural contractions or 6 hours of inadequate contractions with oxytocin used to achieve optimum contractions.
Progressive but slow labour progression should not be considered as an indication for a caesarean delivery.
Previously defined prolonged latent phase of labour of more than 20 hours in nullipara and more than 14 hours in multipara are no longer considered as a factor for caesarean delivery8,9.
3.6.4. Diagnosis of induction failure
This requires that the patient
- Was subjected to complete cervical ripening.
- Has not achieved optimum contraction in spite of oxytocin use.
- Has unsatisfactory cervical dilatation for at least 24 hours with oxytocin use with artificially ruptured membranes. Since induction of labour can take many hours to days and is associated with increased risk of caesarean delivery, it should not be attempted unless obstetrically indicated before 40 weeks.
However, recent literature has shown no difference in the outcome of induction vs expectant management in gestations greater than 39 weeks. Ripening the cervix as a part of the induction protocol has shown to reduce the failure of induction and progress8,9.
3.7. Second stage of labour
This stage begins at complete cervical dilatation of the cervix and ends with the delivery of the neonate. ACOG practice bulletin #49 defines prolonged second stage as two hours for nullipara and one hour for multipara without epidural analgesia. With epidural anaesthesia one hour is added to both categories.
PEOPLE trial and a similar trial in Sweden11 showed that increased duration of the second stage of labour as well as the duration of pushing time, increased the risk of asphyxiation of foetus as well as increased probability of postpartum haemorrhage.
However, a specific absolute total length of second stage over which all women should be considered for instrumental/operative delivery has not been established.
A consensus document developed jointly by ACOG and Society for Maternal-Foetal Medicine recommends22 at least two hours of pushing for multiparous women and 3 hours for nulliparous women before diagnosis of arrest of labour. These timeframes are applicable only if foetal and maternal evaluation continues to be reassuring. Additional time for these time parameters are allowed with epidural analgesia or foetal malposition.
SLCOG recommends ACOG recommendation that advocates a very senior review for the decision to wait any longer.
Second stage of labour consists of passive and active stages.
3.7.1. Passive second stage of labour (descent phase)
- Is diagnosed when full cervical dilatation is reached.
- Bearing down must be discouraged unless the presenting part has reached +1 station.
- Intermittent auscultation of the foetal heart should be done immediately after a contraction for at least one minute, at least every 10 minutes. The maternal pulse should be palpated if there is suspicion of foetal bradycardia or any other FHR anomaly to differentiate the two heart rates.
- Presence of meconium must be noted.
3.7.2. Active second stage of labour (expulsive phase)
- Is diagnosed when the mother gets the urge to bear down with full dilatation and contractions.
- Intermittent auscultation of the foetal heart should be done immediately after a contraction for at least one minute, at least every 5 minutes. The maternal pulse should be palpated if there is foetal bradycardia or any other FHR anomaly.
- Presence of meconium must be noted.
Use of a hand-held Doppler device is recommended (in preference to a Pinnard stethoscope) for foetal heart rate monitoring in the second stage.
Women must be encouraged to continue consuming clear fluids during the second stage.
Support by the labour companion must be continued.
Total time duration allowed for the second stage of labour are as follows:
3.7.2.1 Primigravida
- Birth would be expected to take place within 2 hours of the start of the active second stage in most women.
- Watch for possible delay in the active second stage should be made when it has lasted 1 hour. It is necessary to seek the advice from a health professional trained in the assisted/operative vaginal birth if birth is not imminent.
3.7.2.2. Multigravida
- Birth would be expected to take place within 1 hour of the beginning of the active second stage in most women.
- Watch for possible delay in the active second stage should be made when it has lasted 30 minutes and requires advice from a health professional trained in assisted/ operative vaginal birth if birth is not imminent.
- Delay in the second stage in a multiparous woman must raise suspicion of disproportion or malposition.
One further hour is permitted for women in each category for women with epidural analgesia.
3.7.3. Observations for women and babies in the second stage of labour
All observations should be documented on the Labour Care Guide.
- Chart blood pressure and pulse hourly.
- Continue four hourly temperature recording.
- Vaginal examination must be offered after an hour in the active second stage after abdominal palpation and assessment of vaginal loss.
- Half hourly documentation of frequency of contractions is necessary.
- Consideration of the woman’s emotional and psychological needs addressing.
In addition:
- Assessment of progress should include maternal behaviour, effectiveness of pushing and foetal wellbeing, taking into consideration the foetal position and station at the onset of the second stage. These factors will assist in deciding the timing of further vaginal examination and the need for obstetric review.
- Ongoing consideration should be given to the woman’s position, hydration, coping strategies and pain relief throughout the second stage.
3.7.4. Woman’s position and pushing in the second stage of labour
Although most deliveries in Sri Lanka are conducted in the dorsal/McRoberts position, women may be encouraged to adopt squatting, semi upright or lateral positions to aid the expulsion phase.
Women should be informed that in the second stage, they should be guided by their own urge to push.
If pushing is ineffective, strategies to assist birth such as support, encouragement and change of position is used.
3.7.5. Episiotomy
Where an episiotomy is performed, mediolateral episiotomy, performed at about 40-30 degrees from the midline directed to the right side, (angle is measured taking arbitrary longitudinal line drawn in the perineum going across on all midline orifices connecting in one line as the zero-degree line). (NICE guideline states it as 40-60 degrees but there is no comment on the zerodegree line making it difficult to interpret). Beginning at the vaginal fourchette is preferred to the median episiotomy. It should be performed at the time of crowning of the foetal head.
Episiotomy should be performed after infiltration of 1% lignocaine (up to 20 ml may be used).
In primigravida in whom contractions have become weak and there is no evidence of foetal compromise or obstruction, oxytocin may be administered as an infusion. In this case, the expulsive phase may be continued under close observation for a further 30 minutes. Delivery must be considered at the end of this period.
The mother may continue to consume clear fluids in the active phase.
She must be encouraged to assume any position that she is comfortable in and avoid the dorsal position if necessary.
3.7.6. Women who have the following conditions are recommended to have continuous electronic foetal monitoring
- Significant meconium staining of amniotic fluid,
- Abnormal foetal heart rate detected by intermittent auscultation (< 110 beats per minute; > 160 beats per minute; any decelerations after a contraction)
- Fresh vaginal bleeding
- Maternal pyrexia
In women with spontaneous labour progressing normally; routine early amniotomy and use of oxytocin is not recommended.
3.7.7. Intrapartum interventions to reduce perineal trauma
Either the ‘hands on’ (guarding the perineum and flexing the baby’s head) or the ‘hands poised’ (with hands off the perineum and baby’s head but in readiness) techniques can be used to facilitate spontaneous birth.
A routine episiotomy should not be carried out during spontaneous vaginal birth.
Episiotomy should only be performed selectively in women in whom there is a clinical need, instrumental birth, foetal maneuvering, suspected foetal compromise or a high chance of perineal tears.
3.7.8. Delivery
The foetal head should not be allowed to extend till occiput is felt below the symphysis pubis. The perineum should be supported during delivery of the head. Then the head is delivered with appropriate cleaning of the foetal oropharynx. Woman should be discouraged from bearing down during this period. Following restitution and external rotation, shoulders must be delivered with appropriately directed traction on the foetal head. The baby must be delivered onto the mother’s abdomen. Breastfeeding should be initiated within 30 minutes of birth.
3.8. Third stage of labour
The third stage of labour is the period from complete delivery of the baby to the complete delivery of the placenta and membranes.
3.8.1. Active management of the third stage of labour
Active management of the third stage of labour is recommended for all mothers. This includes;
- Routine use of uterotonic drugs: Oxytocin 5 IUintravenously with the delivery of the anterior shoulder of the baby or 10 IU intramuscularly. If ergometrine is used dose is 0.5mg IV at the delivery of anterior shoulder or same dose intramuscularly.
Oxytocin given intravenously act with one circulation cycle, but action of ergometrine takes 45 seconds when it is given intravenously. Oxytocin given IM work in 5 minutes and ergometrine takes 7.5 minutes for its action when given IM.
- Look for signs of placental separation
- Followed by controlled cord traction.
- Followed by uterine massage.
3.8.1.1. Delayed cord clamping (2 minutes after the birth) and cutting of the cord
Delayed clamping of the cord allows for placental transfusion, which reduces neonatal and infant iron deficiency and anaemia. This policy should be followed unless the baby is born in a poor condition or if the mother is bleeding or risk of Rhesus / any iso immunization is a concern.
3.8.1.2. Controlled cord traction
Clamp and cut the cord close to the perineum. A hand should be placed above the symphysis pubis to stabilize the uterus by applying counter traction during controlled cord traction. Application of cord traction when the uterus is relaxed could lead to acute inversion of the uterus.
After delivering of the placenta it must be placed on a flat surface and its surface should be examined for completeness. On the foetal surface the blood vessels must be traced to exclude a succenturiate lobe. Completeness of the foetal membranes must be ensured.
40-30 degrees from midlne directed to right side (angle is measured taking arbitrary longitudinal line in the perineum going across all midline orifices in one line as the point of zero degrees.) NICE guidelines recommend it as 45-60 degrees however the reference point is not clear.
3.8.1.3. Observations in the immediate postpartum period include
- If the placenta is not delivered by this method, proceed to manual removal of placenta, under suitable anaesthesia.
- Inspect for continued fresh bleeding.
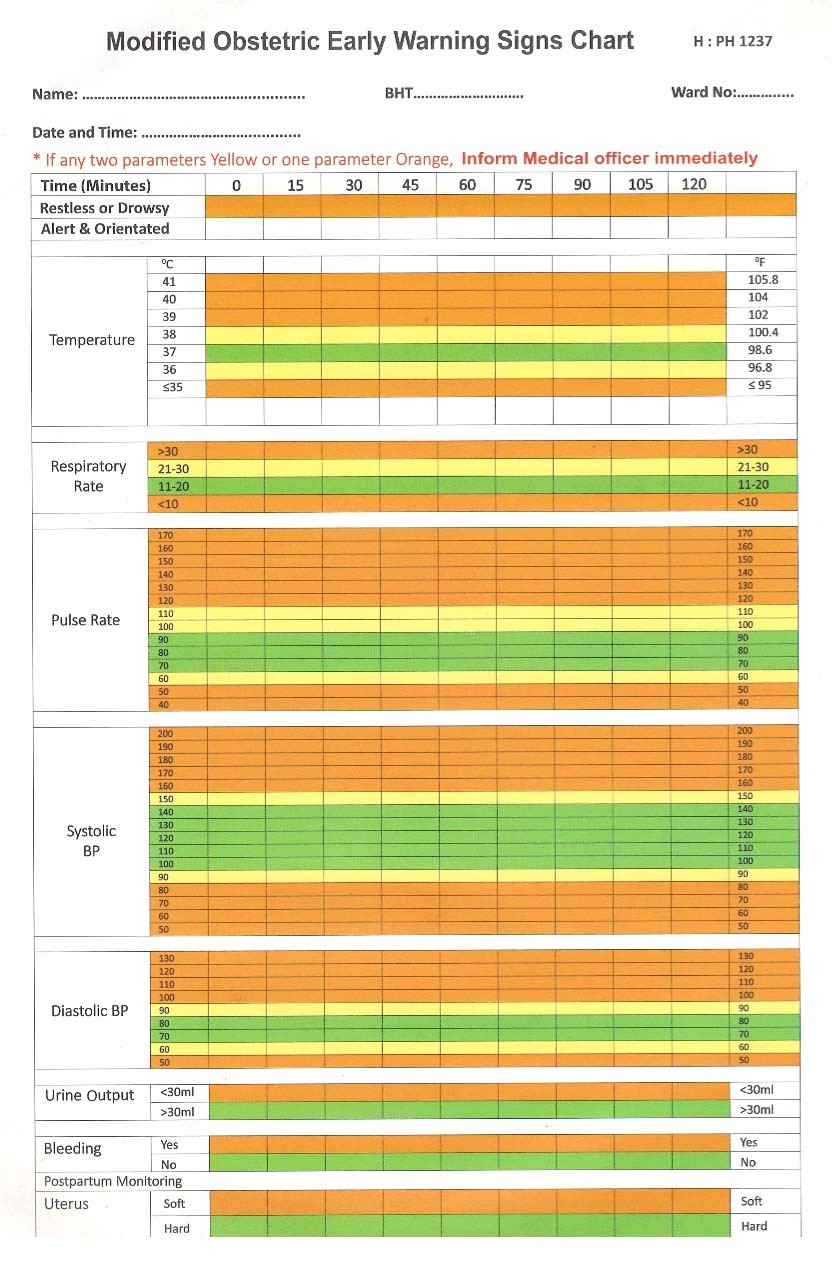
- Start a MEOWS chart. Please see Annexure 3. Check pulse, blood pressure, uterine contraction and the level of the fundus every 15 minutes up to 2 hours.
- Her general physical condition, as shown by her colour, respiration and her own report of how her feels.
3.8.1.3.1. Experienced medical personnel should be informed in any one the following instances
- Continuing fresh bleeding;
- Elevation of the level of the fundus;
- Increase of pulse rate above 100 or by 30 beats per minute; from baseline rate
- Drop in systolic blood pressure below 100 or by 30 mmHg; from baseline pressure
The level of the fundus must be marked on the skin using a marker for observations to be more objective when necessary.
3.8.2. Delayed third stage
Delayed third stage is diagnosed if the placenta is not delivered within 30 minutes of active management.
In managing delayed third stage of labour, options are:
- To proceed with intra-umbilical vein oxytocin, in a dose of 50 IU in 30 ml of 0.9% sodium chloride solution.
A period of 30 minutes is allowed and again controlled cord traction is attempted provided that no ongoing bleeding is observed.
- To proceed for manual removal of placenta with appropriate anaesthesia
3.8.2.1. Induction of labour
Labour induction has increased by 140% since 1990. Several studies on induction of labour associated this observation with increased risk of caesarean delivery. In these studies, the comparison was induced pregnancies with spontaneous labour at the same gestation. This comparison is not fair because the alternative to induction is continuation of the pregnancy but not spontaneous labour. Furthermore, induction is a different physiological process when compared to a woman who is in spontaneous labour.
Definitions of normal spontaneous labour cannot be directly applied to induced labour. A study by Harper and colleagues3 showed that in comparison to normal labour progression, women who were induced had slower progress both for multi and nulliparous in comparison to their counterparts in spontaneous labour. Once reaching 6 cm both induced and spontaneous labour progressed at same rates.
It could be that the studies which showed higher caesarean delivery for induced labour concluded in this manner because they were expecting the induced labour to follow the same curve as spontaneous labour.
3.8.2.2. Labour induction techniques
Taking modified Bishops score into consideration, a score of less than 6 (simple Bishop’s score of 5 or less) is considered to be an indicator predicting poor outcome of induction methods in achieving vaginal delivery.
In this group there are two broad categories. These are
- Women with unfavourable cervix
- Women with favourable cervix
Though not widely used, assessment of the cervix by transvaginal imaging and measurement of Foetal Fibronectin are possible predictors of success of labour induction.
3.8.2.3. Methods of cervical ripening
• Mechanical methods
1. Membrane stripping
Though it is widely practiced, it is not being properly assessed. This is primarily used as a preventive measure for formal induction rather than an induction technique,
2. Balloon catheter
There are various catheters specifically made for the purpose of ripening the cervix but most units use Foley catheters either 16 or 18 gauge for cervical ripening. Taking the low cost of Foley catheters, the results show very encouraging outcome compared to purposemade balloon catheters.
Foley catheter is placed in the extra-amniotic space between the membranes and the internal cervical os. Catheter is then dilated with fluid of 60 to 80 ml of sterile water or saline. The open catheter end is usually closed with a sterile syringe piston of 3 ml size. There is no agreed upon volume of optimal dilatation or the duration to keep in the catheter12.
The experience of SLCOG is that allowing the catheter for spontaneous expulsion of up to 48 hours is safe in the presence of appropriate monitoring regarding infection or membrane rupture. Recent metanalysis shows no additional risk of infectious morbidity associated with this technique13. Recent publication of RCOG advocates even the outpatient use of balloon Foley catheter for induction although SLCOG is advocating only in-ward use of Foley catheter for cervical ripening unless the obstetrician is very confident about the monitoring reliability of the patient.
• Pharmacological methods
Use of prostaglandins could be considered for cervical ripening if there are no pre-existing uterine activity. (i.e. two or more contractions per ten minutes) Prostaglandin E1, i.e. misoprostol and prostaglandin E2 (Glandin E2 vaginal tablet or gel) could be used for cervical ripening.
Although there is no FDA approval, both ACOG and The Society of Obstetricians and Gynaecologists of Canada consider E1, i.e. misoprostol to be both
effective and safe as a cervical ripening agent14,15.
Very recently RCOG recommended the use of misoprostol in doses of 25μg with re-dosing allowed in 6 hours. Redosing at 4 to 6 hours for maximum of 6 consecutive doses has been advocated by WHO16,17 allowed in 6 hours. Although 50μg single dose was more effective than 25μg (single dose) in achieving delivery within 24 hours and a lower oxytocin use, 25μg dose. 25μg dose was safer with lower rate of hyperstimulation, Caesarean delivery for foetal concern and meconium18.
Though E1 could be given sublingually, orally and vaginally, one route has not been shown to have better results in comparison with the other.
Oral misoprostol could have a higher advantage because of consistency in the dosing.
3.8.2.3.1. Prostaglandin E2
The studies have not shown advantage of gel over the tablet. However, most clinicians prefer application of E2 cervical gel. The pessary has an advantage of being able to be removed if hyperstimulation occurs following application.
Contraindications for the use of prostaglandins
- Term pregnancies with prior surgery on uterus
- Existing uterine activity
- Concern about foetal endurance
In this, only removable pessaries should be tried if needed on expert guidance.
Caution is needed if oxytocin to be used within 4-6 hours of use of prostaglandin.
3.8.2.3.2. Oxytocin
One of the most widely used drugs for induction. But the oxytocin’s usefulness as a ripening agent has to be weighed against prolonged time needed for achieving the objective. For this purpose, oxytocin has been shown to be inferior to vaginal prostaglandins19.
Lastly, combination of mechanical and pharmacological agents can be used to achieve the objective of induction of labour. Two randomized studies showed combination of balloon catheter with either misoprostol given vaginally or orally reduced the time to delivery in comparison to treatment with vaginal misoprostol alone20,21. In another study 55 women who received balloon catheter and misoprostol was twice as likely to deliver the baby faster than the woman who received balloon or misoprostol alone.
However, the combination of balloon catheter and oxytocin infusion has shown conflicting results on the efficacy of combination versus using one method alone. Therefore, cannot be recommended by SLCOG other than for research purposes or in rare clinical scenarios.
3.8.2.4. Induction techniques with favourable cervix
- Amniotomy
- Addition of oxytocin to amniotomy
3.9. Fourth stage of labour
This is the time period from the end of third stage until two hours. This is the time for careful monitoring of the maternal parameters for mainly postpartum haemorrhage.
3.9.1. General advice on labour care
The practice of maintaining a labour room ‘Notice Board’ – a ‘White Board’ in which the status of all women in labour is summarised and updated regularly is encouraged. This would convey at a glance to all care providers women who require additional attention. The age, parity status, risk factors, salient findings at each assessment and any abnormalities noted must be included in this.
4. Pain relief in labour
Labour analgesia Objectives
Adequate pain relief Improves the maternal and foetal well-being by minimizing the adverse effects like
- Acidosis
- Dysfunctional labour
- Foetal distress
- Loss of morale and a negative birth experience could have significant long-term effects.
Prenatal education about available analgesic methods can be done in clinics.
It is important to keep the mother informed of the progress of labour and the condition of the foetus throughout the process to get a better support to control pain.
4.1. Methods of pain relief in labour
The selection of the method of pain relief should be based on the patient preference and availability of resources in your institute and contra indications for each method
• Non-pharmacological methods
The advantages of non-pharmacological techniques include their relative ease of administration and minimal side-effects; however, there is little evidence to support the efficacy of many of these techniques, and some may be costly and time consuming.
A selection of non-pharmacological techniques are listed below:
- Transcutaneous electrical nerve stimulation
(TENS);
- Relaxation/breathing techniques
- Temperature modulation: hot or cold packs, water immersion
- Hypnosis
- Massage
- Acupuncture
- Aromatherapy
- Yoga
Breathing exercises, massage and being in water may help to ease pain during the early stage of labour. There is not much evidence that aromatherapy, yoga or acupressure work to relieve pain, but you can use them if the patient wants to.
• Pharmacological methods
- Inhalational methods
Entonox: 50% nitrous oxide in 50% oxygen, provides analgesia within 20-30 seconds of inhalation, with a maximum effect after about 45 seconds.
Advantages are:
- Ease of use
- No requirement for physician supervision
- Minimal accumulation with intermittent use
- Self-administration provides some control
- Relieves labour pain to a significant degree
Disadvantages are:
- Drowsiness, disorientation and nausea may occur including brief episodes of loss of consciousness
(observed in 0.4% of cases after prolonged use)
Does not provide complete analgesia.
4.2. Systemic analgesics
4.2.1. Pethidine: Pethidine is safe and effective in the latent and early active phase. The dose is 1-1.5 mg/kg IM, repeated after 4-6 hours. Administration of a third dose should be done only with the concurrence of senior personnel. It is generally avoided where delivery is anticipated within 4 hours.
Maternal side effects include nausea, vomiting, sedation, dose dependent respiratory depression and a reduction in gastric motility with a subsequent increase in gastric acidity. Therefore, it should be administered coupled with metoclopramide 5 mg IV or 10 mg IM. Neonatal respiratory depression is a recognized consequence as it crosses the placenta. The highest fetal plasma concentration occurs 2-3 hours after maternal IM administration. Naloxone, a pure opioid antagonist should be available for treatment in all facilities administering opioids for analgesia. Naloxone is given to the baby in a dose of 100μg /kg IV. It has a short duration of action and additional doses may be required. If no improvement is seen with the first dose of naloxone, the cause of neonatal respiratory depression is more likely to be a factor other than opioids.
Despite these disadvantages, meperidine remains popular in many obstetric units, is easy to administer and may be a useful analgesic modality where other methods are not available or are contraindicated.
4.2.2. Morphine: Morphine shares many of the sideeffects of meperidine and rapidly crosses the placenta; however, its metabolites do not have convulsant effects. The dose used for maternal analgesia is 0.1-0.15 mg/kg.
4.2.3. Fentanyl: This has a rapid onset of action. It has a longer terminal half-life than both meperidine and morphine, and repeated dosing may result in drug accumulation in both the foetus and the mother. Advantages include absence of active metabolites and rapid onset of action, making it useful for patientcontrolled analgesia.
4.3. Patient-controlled analgesia (PCA)
If regional analgesia is unavailable or contraindicated, then PCA is a useful method of pain control as long as the equipment and staffing are available. It is important that women are instructed on how to use the device effectively.
This itself is associated with greater satisfaction; however,
Many opioids have been used in PCA devices; drugs currently used include fentanyl and, more recently, remifentanil.
A suggested regimen for fentanyl PCA is a 20 µg bolus with 5 minute lockout; however, the ideal loading dose, bolus dose, lockout time and maximum hourly dose remain unclear. Both parturient and neonate should be carefully monitored during labour, and post-partum and PCA settings altered accordingly.
4.3.1. Remifentanil, an ultra-short-acting opioid, does not accumulate, even after prolonged infusions. There are increasing reports of its use in PCA, although, like fentanyl, the ideal regimen remains unclear. A bolus dose of 0.25-0.5 µg/kg with a 2 minute lockout has been used successfully. However, close monitoring is essential and supplementary oxygen may be required.
If an intravenous or intramuscular opioid is used, also administer an antiemetic.
4.4. Regional techniques
Regional techniques represent the “gold standard” for labour analgesia.
Currently, four different neuraxial techniques for labour analgesia:
- Epidural
CSE (Combined Spinal epidural)
- Spinal (Single shot or continuous via catheter) and
DPE (Dural Puncture epidural) techniques aredefined.
4.4.1. Epidural analgesia: is the most effective / gold standard form of pain relief in labour.
- It provides more effective pain relief than other methods.
- It will not increase the length of the first and the passive second stages of labour.
- It may however increase the length of the expulsive phase and increase the likelihood of an instrumental delivery. An additional hour is allowed in the expulsive phase therefore.
- It does not increase the chance of cesarean section
- It does not cause long-term backache.
- It needs to be accompanied by a more intensive level of monitoring. Care and observations for women with regional analgesia in labour.
4.4.1.1. Indications/contraindications
The main indications for epidural analgesia during labour are:
1) Patient choice. 2) Twins.
- Pre-eclampsia.
- Medical comorbidities (eg: high BMI, certain cardiac diseases, predicted difficult intubation).
- Other risk factors for general anaesthetic.
4.4.1.2. Other relative indications
- Augmentation of labour.
- To facilitate foetal blood sampling if patient is unable to tolerate this without an epidural.
4.4.1.3. Absolute contraindications
- Patient Refusal.
- Localised sepsis over insertion site.
- Severe coagulopathy.
- Thrombocytopenia – Plt < 75 109 /L.
- Hypovolaemia /cardiovascular instability.
4.4.1.4. Relative contraindications (discuss with Consultant Anaesthetist):
- Systemic infection.
- Mild coagulopathy.
- Previous lumbar spinal surgery.
4) Certain neurological conditions.
4.4.1.5. Epidural – During 2nd stage pain frequently requires more local anaesthetic for successful relief, and depends on caudal spread of local anaesthetic from the lumbar epidural catheter. However, the dermatomal effects of epidural analgesia may be affected by the level of catheter placement, and caudal spread does not always occur, or takes a prolonged period of time, accounting for sometimes ineffective second stage analgesia.
4.4.2. Spinal – When a woman appears close to delivery, a single injection of local anaesthetic (e.g., bupivacaine or ropivacaine 2-4 mg) with opioid (fentanyl 10-15 μg or sufentanil 1-4 μg) using a 25 or 27 gauge (G) pencil-point spinal needle can provide analgesia for 1-2 h. Its place is limited because of the fixed duration of a single-shot technique, and by the high risk of headache when a large-bore needle is used to place a catheter in the subarachnoid space.
4.4.3. CSE – Combined Spinal Epidural has been shown to provide more rapid, more reliable and more effective analgesia than epidural analgesia, as it provides a more reliable sacral block, leading some practitioners to a strong preference for spinal or CSE procedures in women receiving analgesia late in labour.
CSE techniques performed with high dose spinal opioid (20-25 μg fentanyl) and no local anaesthetic had a higher risk of FHR decelerations (24% compared with 12%) and of uterine hyperactivity (tachysystole) (12% compared with 2%) when compared to CSEs done with local anaesthetic and a lower dose of opioid (fentanyl 10-15 μg).
Foetal bradycardia resulting from a CSE procedure should be managed with maternal blood pressure management and occasionally tocolytic drugs (e.g. terbutaline, nitroglycerine) if tachysystole is suspected, and should rarely lead to emergency delivery. An existing poor FHR tracing is a reasonable factor to consider when deciding between CSE and epidural techniques.
4.4.4. Dural puncture epidural is a recently described technique that can be used when some potential effects of a spinal dose might be inappropriate or undesirable, such as in the case of significant maternal cardiovascular disease or a pre-existing poor fetal tracing. The same technique is used as with a CSE procedure, but no spinal medication is injected after observation of CSF. The backflow of CSF confirms midline epidural placement, one of the technical advantages of the CSE procedure, whereas the lack of spinal dose avoids adverse effects (pruritus, FHR effects, hypotension). Analgesia provided by the DPE technique is more reliable with fewer failed and unilateral blocks compared with an epidural technique. Analgesia, including sacral coverage, may also occur more rapidly because medications are injected into the epidural space translocating into the subarachnoid space via the dural hole.
However, this potential advantage of DPE may depend on the size of the dural hole, and there may be little or no benefit when using needles smaller than 26 G.
Table 1. Advantages and disadvantages of epidural, combined spinal-epidural, and dural puncture epidural analgesia. Indicates some degree of uncertainty. FHR, fetal heart rate
| Epidural | Combined spinal epidural (CSE) | Dural puncture epidural (DPE) |
|---|---|---|
| Advantages | Advantages | Advantages |
| Default technique/long history | ‘Anatomical’ confirmation of | ‘Anatomical’ confirmation of |
| epidural placement | epidural placement | |
| Less equipment/less expensive | Faster analgesia | Stable haemodynamics |
| Stable haemodynamics | Improved analgesia | Faster analgesia |
| ‘Proven’ catheter effect | Better second stage analgesia | Improved analgesia |
| Accidental dural punctures | Better second stage analgesia | |
| Increased maternal satisfaction | Accidental dural punctures | |
| Useful in training environment Need for catheter replacement | Useful in training environment | |
| Disadvantages | Disadvantages | Disadvantages |
| No objective determination of | Paraesthesia (spinal needle) | Larger spinal needle (25G) |
| epidural space | needed | |
| Pruritus | Paraesthesia (spinal needle) | |
| Unreliable second-stage analgesia | FHR effects (hypotension, uterine tone) | Dural puncture for no purpose |
Table 2. Common dosing regimens for neuraxial analgesia in labour. In Europe, levobupivacaine (not available in the USA) may be substituted for bupivacaine at comparable doses.
DPE, dural puncture epidural; PCEA, Patient-Controlled Epidural Analgesia;
PIEB, Programmed Intermittent Bpidural bolus
| Labour spinal dosing Local anaesthetic Opioid Bupivacaine 2.5 μg Fentanyl 10-15 μg Ropivacaine 2.5-3.5 μg Sufentanil 1.5-5 μg Epidural (DPE) loading dose Local anaesthestic Opioid 10-15 ml bupivacaine 0.125% Fentanyl 50-100 μg (50 μg probably enough) 10-15 ml ropivacaine 0.2% Sufentanil 10 μg Epidural infusion (10-15 ml h-1) Bupivacaine 0.0625-0.125% with fentanyl 2 μg ml-1 or sufentanil 0.2-0.5 μg ml-1 Ropivacaine 0.10-0.20% with fentanyl 2 μg ml-1 or sufentanil 0.2-0.5μg ml-1 PCEA recipes (Patient-Controlled Epidural Analgesia) 4-6 ml of infusion drug, lockout 5-10 min, maximum 30-35 ml h-1 total infusion plus boluses PIEB (Programmed Intermittent Epidural Bolus) strategy (essentially replace 10-12 ml h-1 infusion with timed bolus, similar hourly dose, usually with additional PCEA doses) 6-8 ml q 30 min 9-10 ml q 45 min 12 ml q 60 min |
|---|
Adrenaline in concentrations as low as 1:1,000,000 (1-2.2 μg ml-1) may improve analgesia, either by local vasoconstriction maintaining higher concentration of analgesics, or via α2 adrenoceptor-mediated analgesia. Clonidine prolongs the effect of bupivacaine in the epidural space by 25-40% and provides additional analgesia via α2 adrenoceptor agonism.
It can be particularly useful and effective in women with opioid tolerance, where the direct effect of neuraxial opioids or synergism with local anaesthetics may be blunted.
Clonidine can be substituted for fentanyl in similar doses, with similar effects. Preservative-free clonidine 25-100 μg added to an epidural bolus or at a concentration of 2-3 μg ml-1 in standard epidural infusions can supplement analgesia, decrease sacral nerve sparing, improve patients’ satisfaction and reduce the dose of bupivacaine required over the duration of labour.
The most common adverse effect is mild sedation, which can be beneficial in some anxious patients.
4.4.5. Caudal analgesia: Since the development of epidural catheters, caudal epidural injections have become a less popular technique for labour analgesia. Not only do they provide less effective and less flexible analgesia than lumbar epidurals, there is also a higher risk of inadvertent IV injection.
Relief of pain in labour should be a major consideration. The pertinent references for pain management in labour is found under Reference numbers 28, 29, 31, 32 and 33. (Please see ‘References for Management of Pain during Labour’).
5. Care for the new-born baby
Effective care at birth is needed for anticipation of problems with the transition from in-utero dependent life to extra-uterine independent existence and to provide support to ensure stabilization.
- Skilled birth attendant (Medical Officers, Nursing Officers and Midwives) is responsible for the care.
- The care at birth is the same irrespective of birthing place or person attending to the birth.
- At least one health care provider trained in neonatal resuscitation must be physically available at time of birth of all infants irrespective of risk status.
- This person must be present in the delivery room before the birth of the baby.
- The attending personnel should document the baby’s details such as time of birth, weight, gender and any other relevant information in all cases.
The aims of neonatal care following birth include the following:
- Establishment of respiration (as per NRP guidelines)24
- Prevention of hypothermia (Refer to New-born Guideline)25
- Establishment of breast feeding (Refer to New-born Guideline)25
- Prevention of infection (Refer to New-born
Guideline)25
- Detection of danger signs (Refer to New-born Guideline)25
5.1. Following basic steps should be followed at the time of birth;
- Call out the time of birth
- Deliver the baby onto the mother’s abdomen or into her arms
- Dry baby with a warm towel or a warm piece of cloth
- Wipe baby’s eyes
- Assess baby’s breathing while drying
- Make sure that there is no second baby
- Change gloves or remove the first layer of gloves 8. Clamp and cut the umbilical cord
- Put the baby between mother’s breast for skin to skin care
- Place the identity label on the baby
- Cover mother and baby with warm cloth
- Put a hat on baby’s head
The Apgar score at 1 and 5 minutes should be recorded for all births.
Initiation of breastfeeding should be aimed for within 1 hour after birth.
Head circumference, birth weight, length and other measurements should be carried out once the first feed is complete. A healthcare professional should examine the baby to detect any physical abnormality and to identify any problems that require referral.
6. Perineal care
Perineal or genital trauma caused by either episiotomy or tearing need to be repaired.
Before assessing for genital trauma:
- Explain to the woman what you are going to do and why
- Offer analgesia
- Ensure good lighting
- Position the woman so that she is comfortable and the genital structures can be seen clearly.
The initial assessment should be performed gently and with sensitivity and may be done in the immediate period following birth preferably as soon as the placenta is delivered.
6.1. Classification of perineal trauma
- First degree: Injury to skin only
- Second degree: Injury to the perineal body but not the anal sphincter
- Third degree: Injury to the perineum involving the anal sphincter complex
- Fourth degree: Injury to the perineum involving the anal sphincter complex and anal epithelium
Perineal repair should only be undertaken with tested effective analgesia in place using infiltration with up to 20 ml of 1% lignocaine, pudendal block or by topping up the epidural, as soon as possible by a medical officer.
The preferred suture material is Rapidly absorbed Polyglycolic Acid. However appropriate normal polyglycolic acid sutures are to be used for repair of anal sphincter.
The following basic principles should be observed when performing perineal repairs:
- Perineal trauma should be repaired using aseptic techniques.
- Equipment should be checked and swabs and needles counted before and after the procedure.
- Good lighting is essential to see and identify the structures involved.
- Difficult injuries should be repaired by an experienced medical officer in operating theatre under regional or general anaesthesia. An indwelling catheter should be inserted for 24 hours to prevent urinary retention, in such situations.
- Good anatomical alignment of the wound should be achieved, and consideration should be given to the cosmetic result.
- Rectal examination should be carried out after completing the repair to ensure that suture material has not accidently been inserted through the rectal mucosa.
- Following completion of repair, an accurate detailed account should be documented covering the extent of the trauma, the method of repair and the materials used.
- Information should be given to the woman regarding the extent of the trauma, pain relief, diet, hygiene and the importance of pelvic floor exercises.
7. Staffing of the labour room
- At least one medical officer full time should beattached to the labour room.
- Ideally nursing and midwife numbers per shiftshould be maintained as one to one patient.
- Minor staff numbers per shift should be as twoper shift.
- Every six months all staff in the labour room maybe enrolled in simulation practice of all obstetric emergencies’ management.
Achievement of above staffing level is a responsibility of the relevant hospital administration.
8. Equipment necessary for the labour room
- Warm and clean room
- Sufficient examination tables or beds
- Clean linens
- Light source
- Heat source
- Clean and accessible bathrooms for the use ofwomen in labour
- Curtains if more than one bed
Basic Equipment
- Sphygmomanometer or other blood pressuremachine
- Stethoscope
- Body thermometer
- Foetal stethoscope or Doppler
- Hand washing
- Clean water supply
- Soap
- Nail brush or stick
- Clean towel
- Alcohol-based hand rub
The list itemized and revised by Family Health Bureau in 2020 is listed below
Equipment, Furniture and Linen List of basic items needed in labour room for providing EMOC services (300-400 deliveries)
MATERNAL
Basic furniture and general items
| Delivery bed with stirrups | 08 |
|---|---|
| Spot lamps (movable) | 08 |
| Revolving stools | 08 |
| Instrument cabinets (Preferably less than 4 feet) | 02 |
| Wall clock | 01 |
| Emergency drugs trolleys | 01 |
| Patient trolleys | 02 |
| Instrument trolleys | 08 |
| Oxygen cylinder stands and regulators | 04 |
(Continued)
| Wall oxygen (Oxygen cylinders for transfer) | 02 |
|---|---|
| Refrigerator | 01 |
| Rechargeable lamp in emergency (If no generator) | 02 |
| Waste baskets with colour coordination system | 08 |
| Mobile sucker stands for mobile sucker | 01 |
| Chairs | 04 |
| Wheel chair commode Stands for entonox cylinders | 01 |
Surgical equipment
| Sphygmomanometers (medium/large) | 03 |
|---|---|
| Pinard foeal stethoscope/Dopplar | 08 |
| Adult stethoscope | 03 |
| Adult laryngoscope | 02 |
| Ambu bag (adult) | 02 |
| Hand held Doppler (Foetal heart detector | ) 04 |
| CTG machine | 05 |
| Pulse Oxymeter (with paediatric probe) | 01 |
| Hand held disposable vacuum extractors/Hand held vacuum pump | 01 |
| Different size cups | 02 |
| Suction apparatus (adult) | 01 |
| Nebulizer | 01 |
| Defibrillator | 01 |
| Multipara monitor | 01 |
(Continued)
| Patient warmer | 01 |
|---|---|
| Blood warmer | 01 |
| Mini autoclave (If CSSD not available) | 01 |
| Cut down set | 01 |
| Female urinary catheter metal | 05 |
| Surgical drums | 06 |
| Delivery sets | 30 |
| Episiotomy sets | 30 |
| Sets for artificial rupture of members | 20 |
| Cervical repair kit | 06 |
| Perineal repair kit | 02 |
| Specula sims | 04 |
| Specula Cusco’s (large, medium & small) | 02 each |
| Artery forceps | 06 |
| Cheatle forceps | 04 |
| Dressing scissors | 02 |
| Obstetric forceps (Mid cavity) | 02 |
| Wrigley’s forceps | 01 |
| Rotational forceps (high forceps) | 01 |
| Douche can (for use in acute inversion) | 01 |
| Three way tap | 02 |
| Double balloon cervical catheter | 03 |
| Infusion pumps | 06 |
| Kelly’s Forceps | 04 |
| ET tubes 6, 7, 7.5, 8 Patient control analgesia (PCA) pump | 02 |
| Multi parameter monitor | 1per bed |
| Syringe pumps | 1per bed |
| Artery forceps | 02 (Kosher 140 mm straight) |
|---|---|
| Episiotomy scissors | 01 (200 mm curved blut) |
| Umbilical scissors | 01 |
| Kidney trays | 02 or one kidney tray and large rectangle tray to be used for wrapping |
| General surgical towels | 02 – need packing separately |
| Swabs | Adequate amount |
| Sterile pads | 05 |
Delivery packs (each pack to contain)
Episiotomy packs
| Blunt operating scissors | 01 (Mayo 230 mm curved blunt) |
|---|---|
| Needle holder | 01 (Mayo Hagar 180 mm Straight) |
| Toothed dissecting forceps | 01 (250mm straight) |
| Kidney tray | 01 |
| Round body needles/ Cutting needles | 01 each |
| Swabs | Adequate amount |
| GS towels | 02 |
Perineal / cervical repair kit
Sets for artificial rupture of membranes (ARM)
| Long artery forceps | 01 |
|---|---|
| Kidney tray large | 01 |
| Cotton wool | Adequate amount |
| Swabs | Adequate amount |
Other surgical consumables
| Adult endotracheal tubes (Size 6, 7 & 8) | each 01 / adequate amounts |
|---|---|
| IV Cannulae (Different sizes) | Adequate amount / size 14, 16, 17,18 |
| Urinary catheters (Foley catheter) | Adequate amount / 14,16,18 |
| Syringes (Different size) | Adequate amount |
| Suture materials | Adequate amount |
| Vicryl Rapid 0, 2/0, 3/0 | Adequate amount |
| Vicryl 0, 1, 2/0, 3/0 | Adequate amount |
| Distilled water | Adequate amount |
Linen and others
| Gowns | 25 |
|---|---|
| Washable aprons | 12 |
| Sterile mackintosh (1.5 meters) | 24 |
| Boots | 10 sets |
| Sterile vaginal packs | Adequate amount |
| Sterile sanitary pads | Adequate amount |
| Washable curtains | Adequate amount |
| Sterile sanitary pads | Adequate amount |
| Epidural catheter sets (Completed) 18 G | 25 |
Cleaning items
| Anti-Septics | Cleaning-surface-isopropyl alcohol | Adequate amount |
|---|---|---|
| Chlorhexidine for isolation room | Adequate amount | |
| Disinfectant | Floor-sodium hypochlorite/peracetic acid | Adequate amount |
| TCL | Adequate amount | |
| Detergent | Any General-purpose detergent | Adequate amount |
| Reusable equipment - per acetic acid | Adequate amount |
NEONATAL Equipment
| Seca weighing scale | 01 (Preferably digital) |
|---|---|
| Neonatal suckers | 04 |
| Infant Magill’s laryngoscope (straight blade) | 02 |
| Neonatal Resuscitaire | 01 |
| Neonatal cots | 08 |
| Oxygen source | 01 |
| Neonatal stethoscope | 01 |
| Glucometer | 01 |
| BP apparatus with neonatal cups | 01 |
| Guedel airway different neonatal sizes | 04 |
| Neonatal laryngoscope | 02 |
| Low tech Incubator (not necessary if transport Incubator is available) | 01 |
| Rectal thermometer | 05 |
Surgical consumables
| Cord clamps Neonatal Ambu bags | 03 (preferable. Twins need – 2, one for disinfected) |
|---|---|
| Nasogastric tubes Endo tracheal tube (size 2.5, 3.0, 3.5, 4.0) | 02 each |
| Flexible stiletto (for stiffening Endo tracheal tube) | 02 |
| IV Cannulae Pen torch batteries | 05 (buffer stock) |
Linen and others
| Umbilical sets (wrapped in GS towels – to be issued from CSSD) Mackintosh | 24 |
|---|---|
| Masks | 03 |
| Umbilical catheters | 02 |
| Scalpel blades | 02 |
| Catch forceps | 02 |
| Pen torch batteries | 04 |
| EDTA bottles for FBC Plain bottles Microbiological swabs Notice board On call doctor’s information Kidney tray | 01 |
| Sterile gauze packet | 01 |
| Cord scissors | 01 |
Advantages in umbilical sets
- Not using same scissors used for other purposes
- Reduce the incidence of cord infection
- Change the gloves before attending to cord
Cord blood for investigation (RH negative mother)
EDTA bottle to FBC
- Plain bottle (SBR, grouping and RH, Retic count)
Microbiological swabs
To take deep ear swabs for culture
EMERGENCY TRAY – Adults
| ESSENTIAL ITEMS | |
|---|---|
| IV Cannulae (size 14,16,18,20) | Each 01 |
| Disposable syringes 2cc, 5cc, 10cc | Each 01 |
| Oral air way - Size 3 airway | 01 |
| Foley catheters (size 12-14) | Each 01 |
| Adult Laryngoscope - medium long blades | 01 |
| Endo-tracheal tube - 6.5,7, 7.5 mm diameter | 01+introducer |
| Laryngeal mask airway - Size 03 | 03 |
| Adult Ambu bag/ face mask and (scissors, plaster, cotton, gauze swabs) | 01 |
| Suction catheter (16,18,14) gage | 05 from each size |
| Burette set | 01 |
| Suction handles | 01 |
9. Medications
Basic medication list
- Bag of IV fluids
- Oxytocin
- Injectable magnesium sulphate
- Antibiotics
- Antihypertensive medications
- Analgesics
- Anaesthetic medications
- Tamponade catheter
Drugs needed in labour room
ANTIBIOTICS
| Amoxicillin | 250mg, 500mg tab |
|---|---|
| Ampicillin | IV 250mg, 500mg |
| Benzyl Penicillin | 600mg (1 million units vial) |
| Cefalexin | 125mg, 250mg tab |
| Cefotaxime | 1g vial |
| Ceftriaxone | 1g vial |
| Cefuroxime | 750mg vial, 500mg tab |
| Cloxacillin | 250mg, 500mg tab |
| Co-Amoxiclav | 375mg, 625mg |
| Erythromycin | 250mg tab |
| Gentamycin | 20mg in 2ml, 80mg/ml in 2ml ampule |
| Metronidazole | 500mg/ 100ml ampule |
ANALGESIC MEDICATIONS
| Morphine | 10mg, 15mg, 15mg/ml |
|---|---|
| Entonox Bupivacaine HCl (plain) | 10 ml |
| Morphine | 30mg tab |
| Pethidine | 75mg/ 50mg ampule |
| Fentanyl | 100 µg vials |
| Lignocaine | 2% in 20ml vial |
| Paracetamol | 500mg tab/suppositories |
| Diclofenac sodium | 25mg, 25mg, 100mg suppositories |
| Co-codamol (Panadeine) tabs | 500 mg |
| Tramadol Hydrochloride | 50mg tab |
| Tramadol Hydrochloride | 50 mg /2ml ampule |
ANTIEMITIC
| Phenergan (Promethazine) injection | 25 mg |
|---|---|
| Metoclopramide HCl | 10 mg |
| Ondansetron injections/ tabs | 4 mg tablets/ 4 mg IV vials |
UTEROTONICS
| Oxytocin/ Syntocinon injection | 2 units/2 ml, 5 units/ml ampule |
|---|---|
| Ergometrine injection | 0.5mg in 1 ml |
| Oxytocin + Ergometrine Misoprostol | 200 µg tabs |
| Tranexamic acid | 1 g injection |
Treatment of toxicity
| Sodium bicarbonate (NaHCO3) Naloxone Calcium gluconate | 10 ml |
|---|---|
| Intralipid 20% | ampules |
ANTIHYPERTENSIVE MEDICATIONS
| Hydralazine IV/Oral | 50mg tab, 20mg in 1ml ampule |
|---|---|
| Labetalol IV/Oral | 100mg, 100mg in 20ml ampule |
| Methyldopa | 250mg tab |
| Nifedipine (SR) | 20mg |
| Prazosin | 1mg tab |
EMERGENCY DRUGS
IV FLUIDS
5% Dextrose
10% Dextrose
50% Dextrose
Normal saline
Ringer’s lactate
4% Albumin
OTHER DRUGS
| Vitamin K | 1mg in 0.5 ml ampule |
|---|---|
| Heparin | 25000 IU/5 ml ampule |
| Famotidine | 150 mg |
| Rhogam / anti Rho (D) Immune Globulin Vitamin A mega dose | 100,000 IU |
| Ranitidine | 25 mg/ml in 2 ml ampule |
| Metoclopramide | 10 mg tab, 10 mg in 2 ml ampule |
| Cabergoline | 500 mg |
| LMW Heparin (Enoxaparin) | 40/60 mg |
ANTICONVULSANTS
| Magnesium sulphate injection | 10 ml ampule |
|---|---|
| Diazepam injection | 10 mg/2ml |
| Phenobarbital | 15mg, 30mg, 60mg tab |
| Phenobarbital injection | 200mg/ 1ml ampule |
| Levetiracetam midazolam | 5 mg |
TOCOLYTICS
| Nifedipine capsule | 20 mg tab |
|---|
STEROIDS
| Dexamethasone | 0.5 mg tabs |
|---|---|
| Dexamethasone | 8 mg in 2 ml vial, 4 mg in 1ml vial |
| Prednisolone | 5 mg tab |
| Hydrocortisone | 100 IV |
ANTIRETROVIRALS
| Contraceptives |
|---|
| IUD Implants Condoms |
|---|
Waste
- Bucket for soiled pads and swabs
- Receptacle for soiled linens
- Container for sharps disposal
Sterilization
- Instrument sterilizer
- Jar for forceps
For Instrumental deliveries
- Vacuum extractor and KIWI vacuum cups
- Mid cavity, low cavity forceps
Miscellaneous
- Printed Labour Care Guide (Annexure #2) and Meows Chart (Annexure #3)
- Wall clock
- Torch with extra batteries and bulb
- Log book
- Medical records
- Informed consent forms
- Refrigerator
- Basic accommodation for all staff including newly designated medical officer to the labour room
- Power supply
- Food and drinking water
Basic Supplies
- Gloves
- Urinary catheter
- Syringes and needles
- Sterilized blade/scissors
IV tubing
- Suture material for tear or episiotomy repair
- Antiseptic solution (Iodoform or Chlorhexidine)
- Spirit (70% alcohol)
- Swabs
- Bleach (chlorine-based compound)
- Impregnated bed net
- Urine dipsticks, facilities to check urine protein
- Clamps
- Oxygen cylinder/Concentrator
- Emergency trolley
Following items are available as boxes and labelled as
PPH Box – all needed to manage PPH in a box
- Eclampsia and Preeclampsia Box – All needed to manage in an emergency
A separate Neonatal Resuscitation Box with
- Drugs and equipment needed for neonatal resuscitation
- Minimum of two Neonatal Resuscitaires
10. Guidance on environmental infections in healthcare facilities
10.1. Infection control in the labour room
This is very important in the final outcome of labour management. Infections resulting or originating in the labour room should be prevented from adhering to strict protocols and guidelines developed by institutions caring for labour. Input of microbiologist infection control units and administration and the clinicians caring for labor should have policies decided on keeping environment clean and sterile avoiding introduction and cross infection of patients in labour. Following references are suggested for assistance.
Guidance on this subject is provided in Hospital Infection Prevention and Control Manual26 © SLCM 2021, developed by Sri Lanka College of Microbiologists and updated in 2021, Labour Room Chapter 7.4, 155-158.
(Please see Annexure #5)
Guidance on Environmental Infections in Healthcare Facilities27 can be referred to at https://www.cdc.gov/infectioncontrol/guidelines/environmental/index.html as well as
For management of labour in COVID-19 patients, please refer to SLCOG Guidelines of 202128.
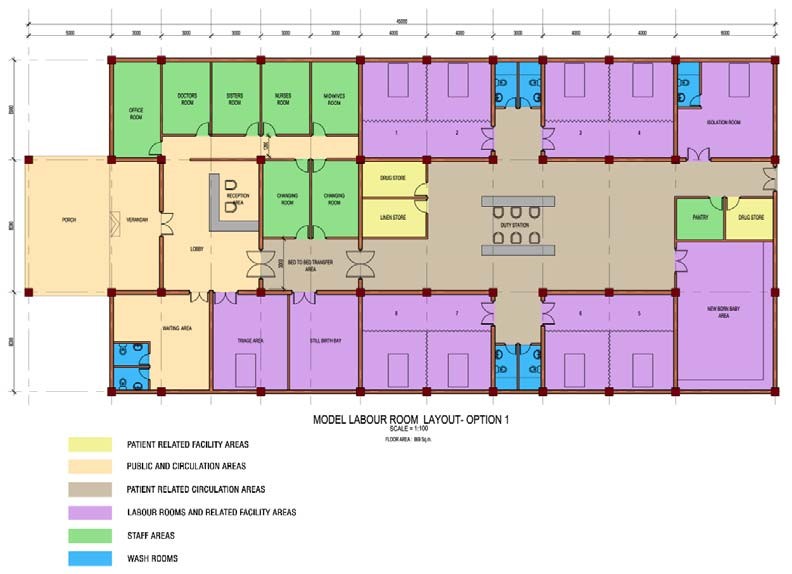
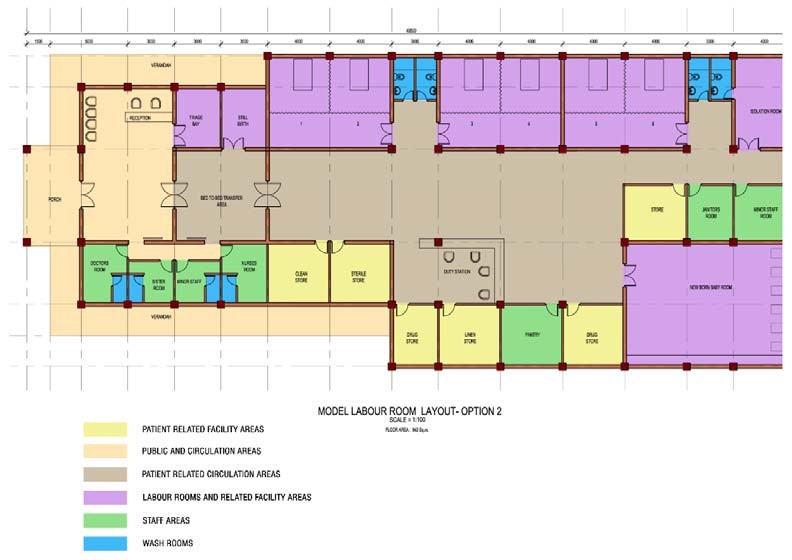
11. Layout plan for a labour suite
Attached herewith is an annexure developed and accepted by the Famiy Health Bureau of Sri Lanka as a suggested layout plan for a labour suite. Please refer to annexure #4.
12. Respectful maternity care during labour and childbirth
WHO recommendations on respectful maternity care during labour and childbirth updated in 2021 can be found at the source https://srhr.org/rhl/article/who-recommendation-on-respectful-maternity-care-duringlabour-andchildbirth
12.1. Communication
A separate line of intercom system should be available 24 hours. When there is no intercom system, a separate landline for the labour room is a must.
Annexure 1.
Contemporary labour curves by parity
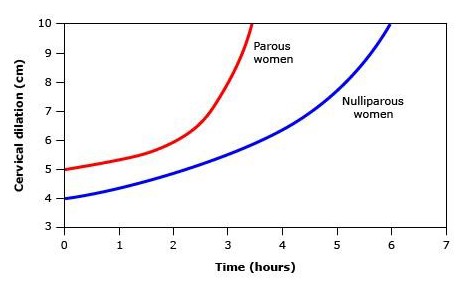
Above is a graphical depiction of average labour curves by parity in singleton term pregnancies with spontaneous onset of labour, vaginal delivery, and normal neonatal outcomes. The main point here is that for parous women, the inflection point for acceleration of cervical dilation is at approximately 6 cm and that there is no clear inflection point for nulliparous women.
Data from: Zhang J, Landy HJ, Branch DW, et al. Contemporary patterns of spontaneous labor with normal neonatal outcomes. Obstet Gynecol 2010; 116:128
Annexure 2.
Annexure 3.
Annexure 4.
Labour room layout
Option 1
Option 2
Annexure 5.

7.4 LABOUR ROOM
Introduction
Infection prevention and control (IPC) measures in the labour room are necessary to reduce the risk of transmission of infections to the mother, newborn and health care workers (HCWs). Potential sources of infections include blood and other body fluids (e.g. amniotic fluid), secretions, excretions, any contaminated equipment, linen and other items used in the labour room or contaminated environment. The risk of these infections can be substantially reduced by simple IPC measures.
7.4.1 Design and layout
Location
- Labour room should be located close to antenatal unit, postnatal unit, blood bank and operating theatre
- In addition, easy access to emergency department and ambulance area is necessary for emergency admission and transfers
Space
- • The most important factor for defining the space and layout of the labor room is the number of labour beds in the unit
- There are two types of labour rooms: Labour rooms with labour-delivery-recovery (LDR) room concept (a pregnant woman spends the duration of labour, delivery, and 4 hours postpartum in the same bed)
- Conventional labour rooms (a pregnant woman is admitted to labour room only at or near full dilation of cervix and is shifted to the postpartum ward after 2 hours)
Functional areas
- Entry/reception area - waiting area, consult/discussion room, storage for wheelchairs
- Handwashing facilities at entries and exits
- Birthing area/suite - assessment/examination rooms, birthing rooms with bath rooms
- Newborn resuscitation room
- Isolation room/s
- Staff station/s
- Support areas - bays for resuscitation trolley, cleaner’s room, clean utility/medication room, dirty utility, washing room
- Store rooms for medication, sterile supplies, equipment and general supplies
- Staff areas - changing rooms with lockers and toilets, meeting rooms, offices, on-call rooms with toilets and showers
- Optional operating room area for emergency caesarean sections
Hospital Infection Prevention & Control Manual © SLCM 2021 155 CHAPTER 7 7.4 LABOUR ROOM
Handwashing area
- Each LDR unit should have one hand washing area with a sink, elbow-operated taps, soap dispenser, single-use towels and a foot operated bin
- Hand washing protocol should be mounted on the wall above the hand washing area
7.4.2 Staffing and discipline
- One to one care for mothers on labour is needed
- Nurses and midwives should undergo a basic training on IPC related to obstetric care at the time of induction and at regular intervals
- One nurse should be appointed as a liaison nurse in IPC for the labour room and she should be responsible for early detection of problems related to IPC and communication with the IPC team
- Labour room attire
- Dedicated clean scrub suits or gown is needed for the labour room staff. These should be changed if visibly soiled
- Water proof disposable apron, gloves, mask, eye protection should be worn by the staff attending to deliveries
- Standard precautions should be practiced by all HCWs before, during and after labour
- Five moments of hand hygiene should be practiced when handling all mothers and neonates Refer Chapter 4.1
- Additional precautions should be taken by HCWs when a patient with an infection is admitted to the labour room Refer Chapter 5
Other measures to prevent infections
- Antibiotic prophylaxis should be administered during vaginal delivery to high risk mothers to prevent Group B streptococcus (GBS) sepsis in the neonate Refer Chapter 13.5
- Vaginal examinations should be kept to a minimum to limit the risk of infection
- Routine perineal/pubic shaving prior to giving vaginal birth is not recommended
7.4.3 Cleaning, disinfection and sterilization of instruments and equipment
- • All surgical items used for the delivery should be properly cleaned and sterilized before reuse. Individual delivery sets should be prepared and sterilized for each patient Refer Chapters 4.5 and 7.1
Table 1. Method of cleaning/disinfection/sterilization of instruments and equipment
| Item | Method of cleaning/disinfection/sterilization |
|---|---|
| Baby cot, warmer and weighing scale | Wipe with 70% alcohol daily and after each use |
| Re-usable metal speculums | Clean with GPD and sterilize by autoclaving before reuse Disposable plastic specula are single use only |
| Mackintosh (contaminated | Immerse in 1% hypochlorite for 30-minute, wash with GPD |
| with blood and body fluids) | and hang to dry |
| Mattresses - with | Wipe thoroughly with GPD in between patients and dry |
| impermeable, intact | Wipe with 1% hypochlorite if contaminated with blood or |
| covering | body fluids |
| Delivery set | Use a sterilized delivery set for each patient. After use, wash instruments with GPD and send for autoclaving |
| Newborn resuscitation | Should be disinfected using a high-level disinfectant |
| equipment | (HLD) or sterilized |
| Newborn resuscitation equipment | Should be disinfected using a HLD or sterilized |
Cleaning, disinfection and sterilization of other patient care equipment/items Refer Chapter 4.5
7.4.4 Environmental cleaning
Table 2. Method of cleaning/disinfection of environmental surfaces
| Item | Method of cleaning/disinfection |
|---|---|
| Floors | Mop three times per day with 0.1% hypochlorite, with dedicated mops for each area. Dry the mops in sunlight and store them dry. Wash mops in 0.1% hypochlorite after each use |
| Walls | Wet mop with GPD weekly |
Cleaning and disinfection of other environmental surfaces and management of spill
Refer Chapter 4.6
7.4.5 Linen
- Linen should be changed in between deliveries
- Linen contaminated with blood and body fluids should be disinfected before sending to the laundry
- Appropriate receptacle to discard used linen should be available in each labour area. Hospital linen management policy should be followed when handling and managing linen Refer Chapter 4.7
7.4.6 Handling and disposal of sharps Refer Chapters 4.4 and 4.8
7.4.7 Waste management
- • Anatomical waste (e.g. placentae and dead fetuses) and clinical waste should be collected separately and should be sent for incineration Refer Chapter 4.8
7.4.8 Occupational health Refer Chapter 9
References
- Maternal health division, Ministry of Health and family welfare, Government of India, 2016. Guidelines for standardization of labour rooms at delivery points. Available at: https://nhm.gov.in/images/pdf/programmes/maternal-health/guidelines/Labor_Room%20Guideline.pdf.
- PATH, 2016. Reprocessing Guidelines for Basic Neonatal Resuscitation Equipment in Resource-Limited Settings. Seattle, Available at: https://path.azureedge.net/media /documents/PATH_reprocessing_ guidelines_basic_neo_resusc_equip3.pdf.
- Shouri, S. and Suchitra, R., 2017. Prevention of Transmission of Infections in Labour Room by Implementing Proper Sterility Techniques and Advising to Follow. IOSR Journal of Dental and Medical Sciences, 16(7), pp.37-39.
- World Health Organization, 2016. WHO recommendations for prevention and treatment of maternal peripartum infections. World Health Organization.
References
- Zang J. Landy HJ, Broach DW., et al contemporary patterns of spontaneous Labour with normal neonatal outcomes. Obstet Gynecol 2011; 118 (1): 29-38.
- Wood AM, Frey HA, Tuuli MG, et al. Optimal Admission cervical dilatation in Spontaneously Laboring Woman. Am J Pernatal 2016; 33 (2): 188-94.
- Harper LM, CAughey AB, Odibo AO, et al. Normal Progress of induced Labour. Obstet Gynecol 2012; 119 (6): 113-8.
- Norman SM, Tuuli MG, Odibo AO. et al, The effects of obesity on the First Stage of Labor. Obstet. Gynecol 2012; 120 (1): 130-5.
- Spain JE, Tuuli M. Caughey AB, et al Normal First Stage of Preterm Labor. Am J. Perinatal 2014; 31(4): 315-20.
- Sondgerath KE, Stout MJ, Graseck AS. et al Progress of induced labor in trial of labor after cesarean delivery. Am J Obstet Gynecol 2015; 213 (3): 420. e1-5.
- Graseck A, Tuuli M, Roel K. et al Fetal descent in labor. Obstet Gynecol 2014; 123 (3): 521-6.
- Spong CY, Berghella V. Wenstrom KD, et al Preventing the first cesarean delivery: Summary of a joint Eunice Kennedy Shriver National Institute of Child Health and Human Development, Society for Maternal-Fetal Medicine, and American College of Obstetricians and Gynecologists workshop. Obstet Gynecol 2012; 120 (5): 1181-93.
- Caughey AB, Cahill AG, Guise JM. et al. Safe prevention of the primary cesarean delivery. Am J Obstet Gynecol 2014; 210 (3): 179-93.
- Graseck AS, Adibo AO, Tuuli M, et al. NormalFirst Stage of Labour in women undergoing trial of labour after caesarean delivery. Obstet Gynecol 2012; 119 (4): 732-6.
- Looft E, Simic M, Ahlberg M, et al. Duration ofsecond stage labour at term and pushing time risk factors for postpartum haemorrhage. Paediatr Perinat Epidemiol 2017; 31: 126-33.
- Gu N, Ru T, Wang Z, et al. Foley catheter forinduction of labor at term: an open-label, randomized controlled trial. PLoS One 2015; 10 (8): e0136856.
- McMaster K, Sanchez-Ramos L, Kaunitz AM.
Evaluation of a transcervical Foley catheter as a source of infection. Obstet Gynecol 2015; 126(3): 539-51.
ACOG Committee on Practice BulletinsObstetrics, ACOG Practice Bulletin No. 107: Induction of labor, Obstet Gynecol 2009; 114 (2 Pt 1): 386-97.
- Leduc D, Biringer A, lee L, et al, Society ofObstetricians and Gynaecologists of Canada. Induction of labour. J Obstet Gynaecol Can 2013; 35(9): 840-60.
- Tang J, Kapp N, Dragoman M, et al. WHOrecommendations for misoprostol use for obstetric and gynecologic indications. Int J Gynaecol Obstet 2013; 121(2): 186-9.
- Kundodylwa TW, Alfirevic Z, Weks AD, Low-doseoral misoprostol for induction of labor: a systematic review. Obstet Gynecol 2009; 113(2 Pt 1): 374-83.
- McMaster K, Sanchez-Ramos L, Kaunitz AM.Balancing the efficacy and safety of misoprostol: a meta-analysis comparing 25 versus 50 micrograms of intravaginal misoprostol for the induction of labour. BJOG 2015; 122(4): 468-76.
- Alfirevic S, Kelly AJ, Dowswell T Intravenousoxytocin alone for cervical ripening and induction of labour. Cochrane Database Syst Rev 2009; (4): CD003246.
- Carbone JF, Tuuli MG, Fogertey, PJ, et al.Combination of Foley bulb and vaginal misoprostol compared with vaginal misoprostol alone for cervical ripening and labor induction: a randomized controlled trial. Obstet Gynecol 2013; 121(2 Pt.1) 247-52.
- Hill JB, Thigpen BD, Bofill JA. et al. A randomizedclinical trial comparing vaginal misoprostol versus cervical Foley plus oral misoprostol for cervical ripening and labor induction. Am J Perinatol 2009; 26(1): 33-8.
- Caughey AB, Cahil AG, Guise JM, et al. ACOG/SMFM Obstetric Care Consensus. Safe prevention of the primary caesarean delivery. Obstet Gynecol 2014; 123: 693-711.
- ACOG Committee on Practice BulletinsObstetrics, ACOG Practice Bulletin No 209: Obstetric Analgesia and Anesthesia. Obstet Gynecol. 2019; 133(3): e208-e225.
- Rajendra PA, Pawale D, Murki S. NRP 2020: Changes, implications for practice and concerns
for developing countries Sri Lanka Journal of Child Health, 2021; 50(2): 329-33.
2020 National Guidelines for Newborn Care Revision 2020; Family Health Bureau, The Sri Lanka College of Paediatricians 2014; ISBN 978955-1503-65-9.
- Hospital Infection Prevention and Control Manualby Sri Lanka College of Microbiologists, Chapter 7. 2021; 155-8.
- Guidelines for Environmental Infection Control inHealth-Care Facilities, Recommendations of CDC and the Healthcare Infection Control Practices Advisory Committee (HICPAC) U.S. Department of Health and Human Services Centers for Disease Control and Prevention (CDC) Atlanta, GA 30329, 2003; Updated: July 2019.
- SLCOG Guideline on Management of COVID-19 in Pregnancy: Sri Lanka College of Obstetricians and Gynaecologists 2021; https://www.slcog.lk/ wp-content/uploads/2021/05/guideline-on-covid-
19-in-pregnancy.pdf
References on Management of Pain during Labour
- Intrapartum care for healthy women and babies;NICE Clinical guideline, December 2014 and updated 2017; www.nice.org.uk/guidance/cg190
- Shatil B, Smiley R, Neuraxial analgesia for labour,Review Article BJA Educ 2020 Mar; 20(3): 96102. doi: 10.1016/j.bjae.2019.11.006. Epub 2020 Jan 27.
KK Lam, MB, et al. Labour analgesia: update andliterature review, Hong Kong Med J 2020 Oct; 26 (5): 413-20.
- Sri Lanka College of Obstetrics and GynaecologyGuidelines; Management of Normal Labour; Sri Lanka Journal of Obstetrics and Gynecology, 2022.
WHO recommendation on epidural analgesia forpain relief during labour, 2018; https://srhr.org/rhl/ article/who-recommendation-on-epidural-
analgesia-for-pain-relief-during-labour